
The best way to manage deviations in clinical research is to hold every deviation as one structured record that links the event to its subject, visit, site and study, applies the same classification criteria at every site, and connects directly to its root cause and CAPA. Trends then surface across studies before an inspection finds them.
A protocol deviation is any departure from the approved study protocol, whether planned or unplanned. It may involve missed procedures, incorrect dosing, out-of-window visits, or incomplete documentation. Each deviation must be assessed for its impact on participant safety and data integrity, in line with GCP expectations.
In practice, most deviations do not originate from isolated errors. In fact, deviations emerge from protocol complexity, execution gaps, and disconnected processes across teams responsible for study delivery.
So, effective deviation management depends on structured processes, consistent classification, and connected operational control across the study lifecycle.
AQ’s guide to deviation management explains:
- what protocol deviations are
- how they are classified
- what causes them in real-world studies
- and how research teams can manage them effectively with a more connected system
Also Read: What is an eTMF in Clinical Trial Research?
What Does Effective Protocol Deviation Management Require?
Effective protocol deviation management requires a controlled structure where deviations are identified consistently, recorded accurately, analysed with clear linkage to root cause, and tracked through to resolution with full visibility across teams. Each element must remain aligned across studies to maintain compliance, data integrity, and inspection readiness.
- consistent definition and classification based on impact on safety and data
- contemporaneous, complete, and traceable documentation
- clear linkage between deviation, root cause, and CAPA
- visibility into deviation status, trends, and recurrence across sites
- defined ownership for review, action, and closure
- aligned protocol understanding across investigators, coordinators, and quality teams
- connected operational control across documentation, quality, and study activity
Also Read: What is QMS (Quality Management System) in Clinical Research?
What Is the Difference Between a Protocol Deviation and a Violation?
A protocol deviation is any departure from the approved protocol. A violation is a local label some sponsors apply to a deviation that affected participant safety, participant rights or the reliability of the data. ICH E6(R3) recognises deviations and important deviations, so the word violation carries only the meaning a sponsor procedure gives it.
Research teams search for protocol deviation vs violation because the two words travel together in training material and sponsor templates. Only one of them appears in the guideline. ICH E6(R3), the final Step 4 version of the Good Clinical Practice guideline adopted on 6 January 2025, states at section 2.5.3 that the investigator should document all protocol deviations, and should explain those deemed important. Section 3.9.3 places the classification decision with the sponsor, which should determine the trial-specific criteria for classifying protocol deviations as important.
| Term | What It Describes | Where the Label Comes From | What It Changes |
| Protocol deviation | Any departure from the approved protocol, planned or unplanned | ICH E6(R3) section 2.5.3 | The investigator documents it |
| Important deviation | A deviation that meets the sponsor trial-specific criteria for importance | ICH E6(R3) section 3.9.3 | The investigator explains it and the sponsor reviews it |
| Protocol violation | A sponsor or site term for a deviation that affected safety, participant rights or data reliability | The sponsor procedure or the local site SOP | Local escalation, unless the sponsor criteria also make it important |
| Serious breach | A breach of GCP or the protocol that the sponsor is required to notify | MHRA good clinical practice inspections guidance on GOV.UK, last updated 22 September 2026 | A notification to the MHRA |
The practical consequence sits in the last two rows. A local label changes who reviews the record inside the organisation. The serious breach threshold changes who outside the organisation has to be told, and the MHRA guidance Clinical trials for medicines: Good clinical practice inspections, published on GOV.UK on 18 December 2014 and last updated on 22 September 2026, states that you must notify the MHRA of serious breaches of GCP or the trial protocol. Our guide to when an error becomes a deviation or a CAPA sets out that threshold in full.
What Belongs in a Protocol Deviation Log?
A protocol deviation log holds one row per event, with the study, site, subject, visit, the protocol requirement that was missed, the date of occurrence, the date of discovery, the classification, the root cause, the CAPA reference and the closure signature. Every entry carries a time stamp and a named author.
| Field | What It Records | Why an Inspector Asks for It |
| Deviation ID | One unique reference per event | It is the key that ties the log to the CAPA record and the site file |
| Study, site, subject, visit | Where in the trial the departure happened | It allows the event to be placed against study activity and clinical data |
| Protocol requirement missed | The section, window or criterion that was departed from | It shows the departure was measured against the approved protocol version |
| Date of occurrence | When the departure happened | It fixes the event in the participant timeline |
| Date of discovery | When the site became aware of it | It shows how long the departure ran undetected |
| Classification | Important or not important, against the sponsor criteria | It shows one standard applied across every site on the trial |
| Impact assessment | The effect on participant safety and on data integrity | It is the judgement the investigator is accountable for |
| Root cause | The process or condition that allowed the departure | It is the only field that explains repeats |
| CAPA reference | The link to the corrective and preventive action record | It proves the finding was acted on rather than logged |
| Owner and status | The named person accountable and the current state | It shows open items have an owner rather than a flag |
| Closure record | The signature, date and effectiveness evidence | It completes the chain an inspector follows end to end |
Two of these fields carry more weight than the rest. The date of occurrence fixes the event against study activity. The date of discovery shows how long the departure ran before anyone saw it. A log that carries one date and not the other leaves the detection question open, and detection is the question an inspector asks after the event itself is established.
Also Read: CAPA Effectiveness Verification: Proving the Fix Held
Why Do Traditional Approaches Fail to Manage Deviations in Clinical Research?
Traditional approaches fail because deviation management remains fragmented across systems, delayed in documentation, inconsistent in classification, and disconnected from root cause and CAPA tracking. Deviation records exist, but they do not stay aligned with study activity, quality processes, and follow-up actions. This limits visibility, delays resolution, and allows repeat issues to continue across sites.
Let us explain this using an example.
Protocol Deviation Examples From One Treatment Cycle
The protocol deviation examples below all come from one study and one treatment cycle. Reading them together shows the pattern that a single log entry hides.
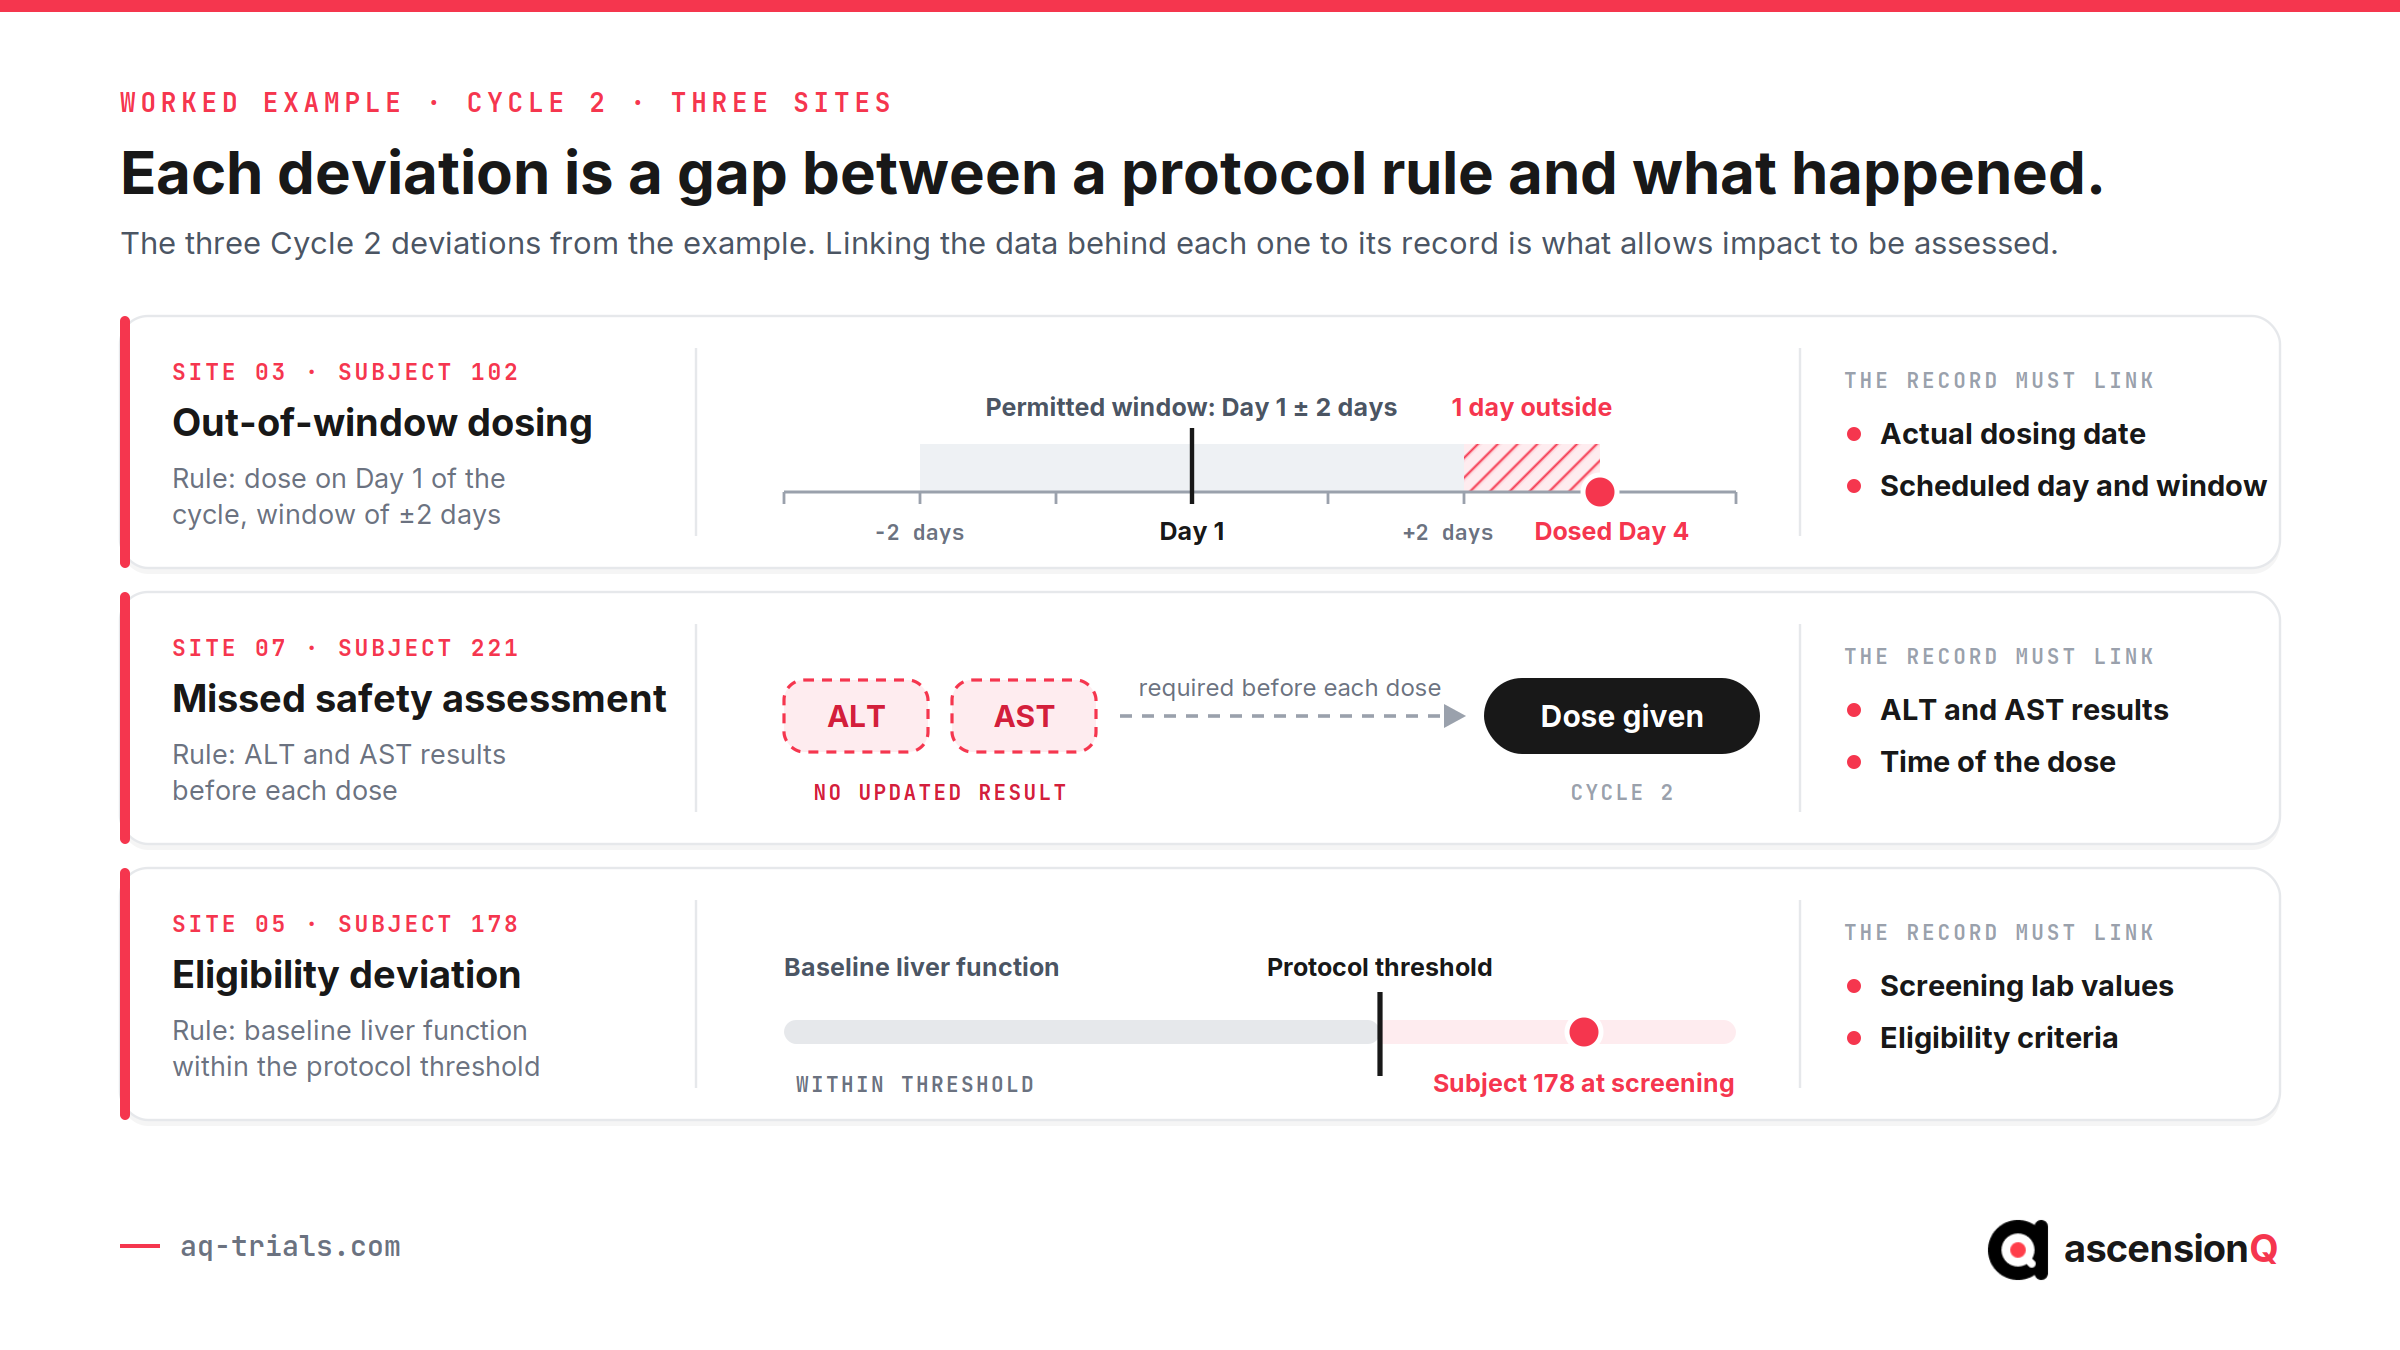
For instance, you are managing a Phase III oncology study for metastatic lung cancer across 10 sites in the UK and EU. The protocol defines dosing on Day 1 of a 21-day cycle, a visit window of ±2 days, mandatory ALT and AST results before each dose, and strict eligibility criteria based on baseline liver function.
During Cycle 2, multiple deviations occur across sites. At Site 03, Subject 102 receives dosing on Day 4 instead of Day 1, which creates an out-of-window dosing deviation. At Site 07, Subject 221 receives dosing without updated ALT and AST results, which creates a missed safety assessment deviation. At Site 05, Subject 178 is enrolled with liver function values outside the protocol threshold, which creates an eligibility deviation. Each of these directly affects protocol compliance, participant safety, or data integrity.
Now, these deviations are handled using typical processes. Site 03 records the event in an Excel deviation log. Site 07 updates CTMS after the monitoring visit. Site 05 documents the issue through email and later uploads it to eTMF. Classification differs across sites, where one marks the deviation as minor, another marks a similar case as major, and another leaves it unclassified. Root cause is recorded as scheduling issue, lab delay, or screening oversight. CAPA actions such as retraining staff or updating checklists are tracked in a separate system without direct linkage to the original deviation.
This approach does not provide control. It only impacts documentation.
- deviation data remains spread across systems without a single view
- classification varies, so risk and priority remain unclear
- documentation timing does not match actual study activity
- root cause does not explain repeat patterns
- CAPA actions remain disconnected from deviation trends
It will only impact oversight and delay resolution. It will also cause repeated deviations across sites, slow identification of high-risk patterns, incomplete inspection readiness, and increased audit findings.
However, if you adopt a more controlled and connected approach, deviation management remains aligned across the study. Deviation records stay standardised across sites, classification follows the same criteria, documentation reflects real-time study activity, root cause links directly to CAPA, and trends remain visible across all sites. This improves control, reduces repeat deviations, and supports consistent inspection readiness across the study lifecycle.
Also Read: What is CTMS
Best Ways to Manage Deviations in Clinical Data Management
Effective deviation management in clinical data management depends on how deviation data is structured, captured, connected, and reviewed across the study. Control improves when deviation records remain consistent across sites, aligned with clinical data, and traceable through root cause and follow-up actions.
Notably, a controlled approach to deviation management in clinical research requires:
- Maintain one structured deviation record per event
Each deviation must exist as a single, standardised record with defined data fields. The record should link directly to subject ID, visit, site, and study to ensure traceability across datasets and systems. - Capture deviation data at the time of occurrence
Deviation entries must reflect actual study activity. Delayed or retrospective documentation creates gaps in timelines and weakens audit trails. Contemporaneous capture ensures accuracy and regulatory alignment. - Apply consistent classification across all sites
Classification must follow the same criteria for important and non-important deviations across CRO, sponsor, and site teams. Consistency ensures correct prioritisation and supports meaningful comparison across sites. - Link deviation data with clinical data and study outcomes
Deviation records should connect with relevant clinical data points such as dosing, lab values, and visit schedules. This linkage allows assessment of impact on participant safety and data integrity. - Connect deviation records with root cause analysis and CAPA
Root cause and corrective actions must remain directly linked to each deviation record. This ensures that identified issues are addressed at source level and that preventive actions can be tracked over time. - Enable cross-site and cross-study trend visibility
Deviation data must support aggregation and analysis across sites and studies. Visibility into frequency, recurrence, and patterns helps identify high-risk processes and supports early intervention. - Maintain complete and traceable audit trails
Every deviation record must include time-stamped entries, updates, and status changes. Traceability ensures readiness for audit and supports regulatory expectations for transparency.
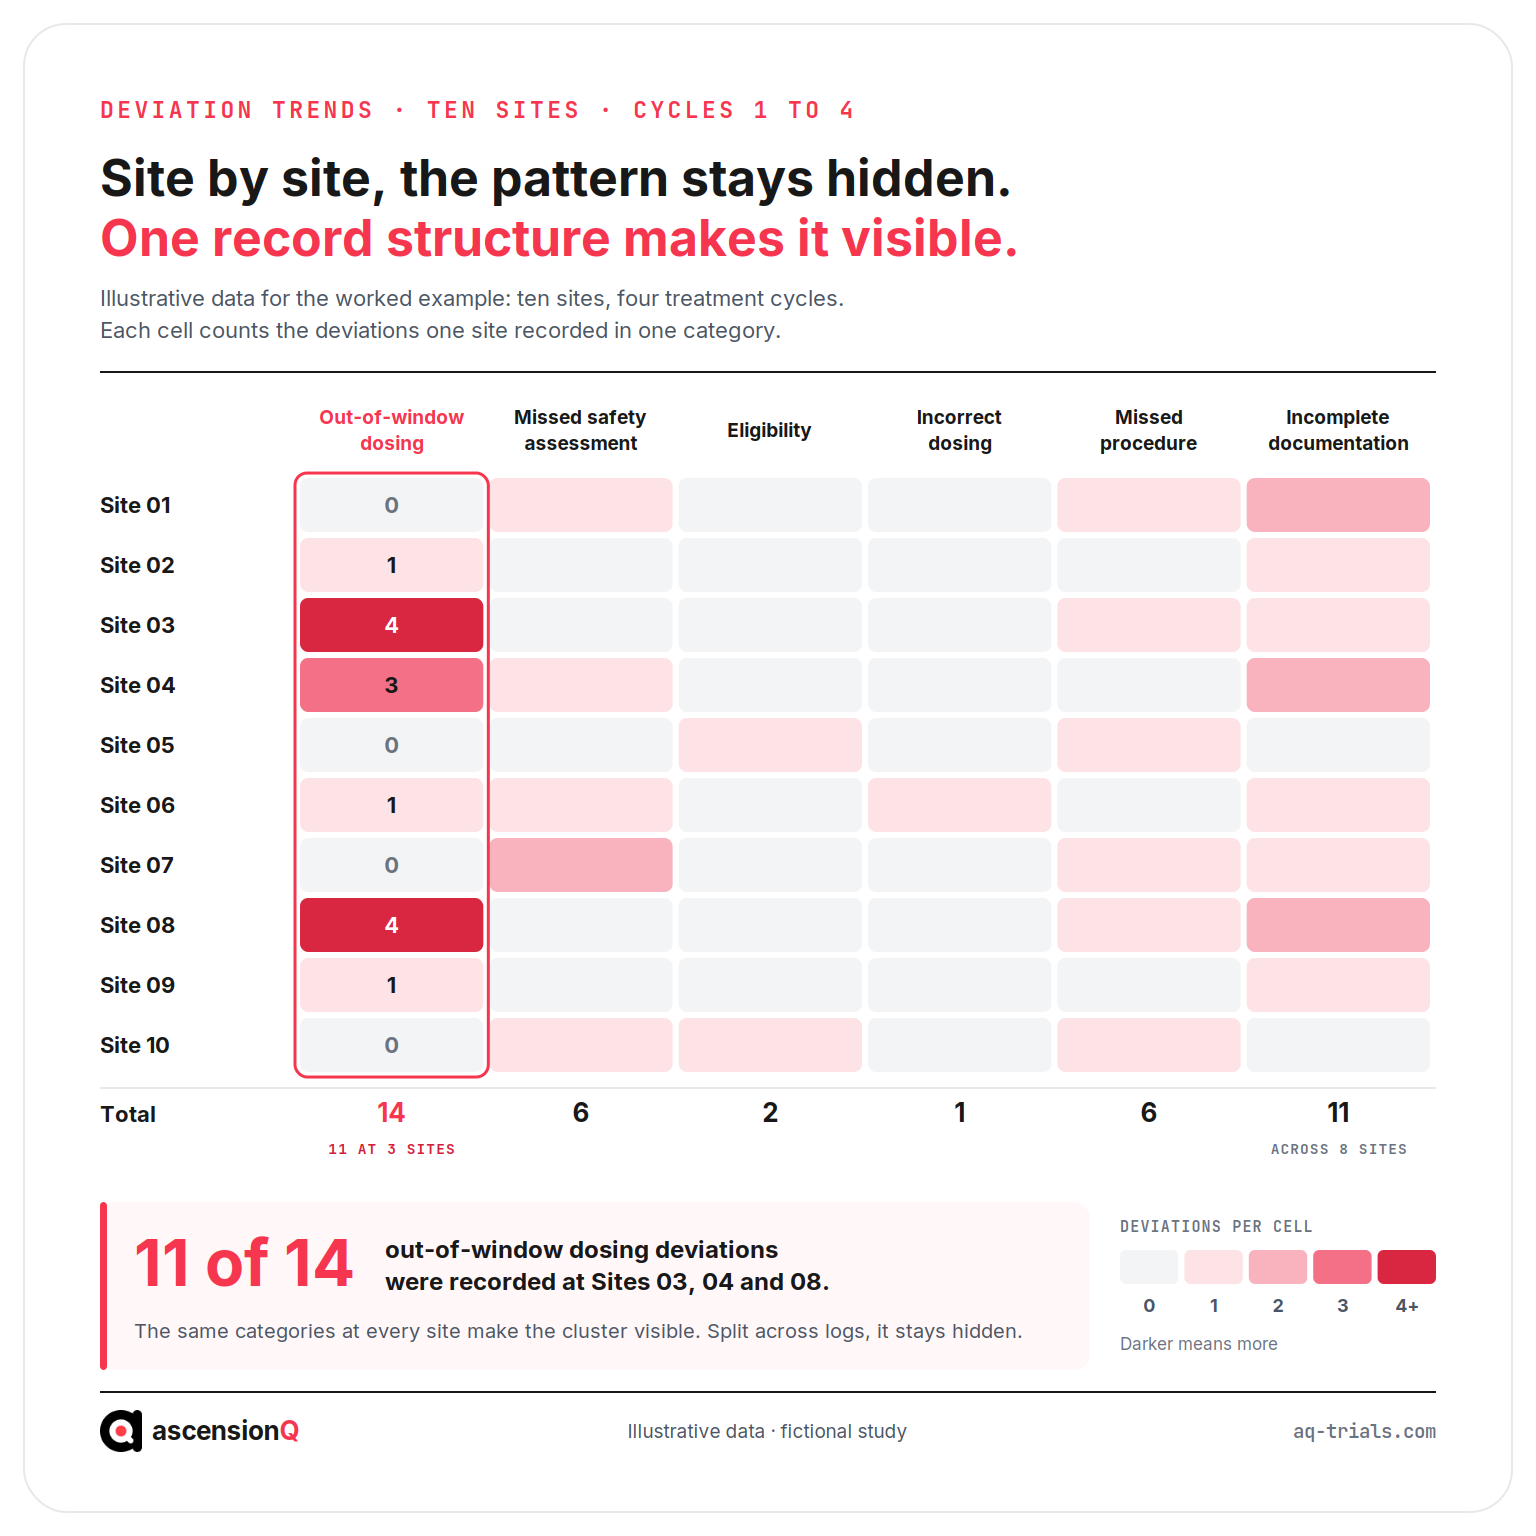
In short, you need a structured and connected deviation management framework with consistent recording, clear classification, direct linkage to root cause and CAPA, and full visibility across sites, systems, and study activities.
Also Read: What is DOA: Delegation of Authority in Clinical Research
How Do I Manage Deviations and CAPA Across Multiple Trials?
Deviations and CAPA across multiple trials are managed from one record set with one classification scheme, reviewed on a schedule that reads the whole portfolio rather than each study alone. A cause that appears in two studies is a process failure at the organisation, so the CAPA is raised against the process.
How Does a Deviation at One Site Become a Programme-Level Signal?
A deviation starts as one event at one site. It becomes a signal at the next level up when the same cause appears again somewhere else. The escalation runs through three readings of the same data, and each reading needs a different record to confirm it.
| Level | What the Data Shows | The Record That Confirms It | Who Reviews It |
| One event | A single departure with a local cause, such as one mis-booked appointment | The deviation record and its impact assessment | The investigator and the study coordinator |
| Cross-site pattern | The same deviation category clustering at a few sites on one study | The deviation log aggregated by site and category | The study quality lead and the sponsor |
| Cross-study signal | The same root cause appearing on unrelated studies | The CAPA record set read across the portfolio, with the training file and the delegation log | The organisation quality function |
The second reading is the one most sites already do. The third is the one that gets missed, because it needs deviation records from different studies to sit in the same structure with the same classification. Separate logs per study make the comparison manual, and a manual comparison happens after a finding rather than before one.
How Often Should Deviation Trends Be Reviewed Across Studies?
ICH E6(R3) sets the expectation at section 3.10, where the sponsor should implement an appropriate system to manage quality throughout all stages of the trial process, and should adopt a proportionate and risk-based approach to quality management. Two provisions underneath it govern the review itself.
- Section 3.10.1.3 asks the sponsor to set pre-specified acceptable ranges where relevant, and states that an evaluation should be performed to determine if there is a possible systemic issue once a range is exceeded
- Section 3.10.1.5 asks the sponsor to review risk control measures periodically, which makes the review a scheduled activity with a date rather than a response to a finding
A portfolio review needs a fixed cadence written into the quality system, and a defined threshold for each deviation category that triggers the systemic evaluation. The cadence an organisation chooses matters less than the fact that the review runs on a date. A review that only happens after an audit finding is a response, and a response arrives too late to prevent the recurrence it describes.
When Does a Single Deviation Become a Systemic CAPA?
One deviation justifies a correction. It justifies a systemic CAPA when the cause sits in a process that more than one study depends on. Four tests settle it.
- The same root cause already appears on another deviation record, on this study or another one
- The cause sits in a shared process such as training, scheduling, delegation or document control, rather than in one person on one day
- The control that should have caught the departure is absent across every study, which means the next study inherits the same gap
- The same category recurs after a completed action, which shows the earlier fix treated a symptom
A systemic CAPA is raised against the process and verified across the studies that use it, so the effectiveness check has to look wider than the study where the deviation was first found. Our worked CAPA example follows one deviation through all seven stages with dates and named artefacts, including the root cause analysis and the effectiveness check.
AQ CAPA holds every record on one platform with the site file and the quality system, so a repeat finding across studies is visible without reconciling systems.
Traditional vs Connected Protocol Deviation Management
Traditional deviation management relies on separate tools, delayed updates, and manual coordination across teams. Each step, from identification to CAPA, operates in isolation, which limits visibility and slows resolution. A connected approach aligns deviation data, analysis, and follow-up within one operational structure, which improves traceability, consistency, and study control.
| Area | Traditional Approach | Connected Approach |
| Deviation Recording | Multiple logs across Excel, CTMS, and emails | One structured record within a single system |
| Documentation Timing | Entered after monitoring or review | Captured at the time of occurrence |
| Classification | Varies across sites and teams | Standardised criteria applied across all sites |
| Root Cause Analysis | Generic and recorded separately | Structured and directly linked to each deviation |
| CAPA Management | Tracked in separate tools | Integrated with deviation and RCA workflows |
| Visibility | Limited view across systems | Unified view across sites, teams, and studies |
| Trend Analysis | Manual and delayed | Real-time pattern identification |
| Audit Readiness | Requires manual compilation | Maintained through complete, traceable records |
Also Read: eQMS vs DMS in Clinical Trials
AQ Platform: Manage Protocol Deviations Within One Connected System
AQ connects study operations, documentation, and quality processes into one clinical research environment, which brings deviation-related activity into a single, aligned operational flow. Study events, supporting records, and quality actions stay connected, so deviation identification, review, and follow-up reflect actual study execution without reliance on separate trackers or manual reconciliation.
- study activity in CTMS provides a clear view of visits, dosing, and milestones, which supports timely identification of deviation events
- eTMF and eISF maintain structured, version-controlled documentation, which ensures complete and inspection-ready records
- AQ Pharmacy aligns pharmacy and investigational product data with study activity, which supports full context for deviation assessment
- QMS aligns deviation review, classification, and governance within controlled quality processes
- CAPA workflows connect directly with quality events, which supports consistent follow-up and prevention of recurrence
- Digital DoA defines responsibility and ownership across investigators, coordinators, and quality teams
Ultimately, AQ’s connected structure keeps deviation-related data, analysis, and follow-up aligned across the study lifecycle, which improves visibility, strengthens control, and supports consistent inspection readiness.
A live walkthrough shows a deviation raised at site level, classified, routed for quality review, and connected to the CAPA that follows it, with the full history retained for inspection. Book a live demo to see how AQ manages deviations end to end.
Frequently Asked Questions
What is the difference between a protocol deviation and a violation?
A protocol deviation is any departure from the approved protocol, planned or unplanned. A violation is a local term for a deviation that affected participant safety, participant rights or data reliability. ICH E6(R3) names deviations and important deviations only, so the sponsor criteria decide which label a site applies and what follows from it.
What belongs in a protocol deviation log?
One row per event, carrying the study, site, subject, visit, the protocol requirement that was missed, the date of occurrence, the date of discovery, the classification against the sponsor criteria, the root cause, the CAPA reference and the closure signature. Each entry needs a time stamp and a named author, so the audit trail shows who recorded what and when.
When does a deviation become a CAPA?
A deviation becomes a CAPA when its cause sits in a process rather than a single event. Two deviations sharing one root cause, a control that is missing across studies, or a repeat after retraining all meet that test. ICH E6(R3) section 3.10.1.3 asks for an evaluation to determine whether a possible systemic issue exists.
What are examples of protocol deviations?
Common examples include a dose given outside the protocol visit window, a dose given without the mandatory safety bloods, a participant enrolled outside the eligibility criteria, a missed procedure at a scheduled visit, consent taken on a superseded version, and an IMP stored outside its specified range. Each one is assessed for its effect on participant safety and on data integrity.
