
CAPA management software in clinical research is the controlled system that holds each corrective and preventive action record and enforces the sequence that record has to follow. It ties a quality event to its investigation, root cause, actions, effectiveness check and signed closure, so an inspector can follow the whole resolution in one place.
Quality failures in clinical research rarely surface without early warning signs. Delegation logs remain unsigned for weeks. Investigational products get dispensed outside approved storage windows. The same data entry discrepancy appears again during monitoring, even after previous corrective steps. Every issue leads to documentation, internal discussions, and sometimes formal findings. In many cases, identical operational gaps continue repeating across sites, studies, or departments.
Corrective and Preventive Action (CAPA) management exists to stop that cycle. Structured CAPA processes turn quality events into documented, investigated, verified, and fully resolved outcomes. It captures what went wrong, investigates why, defines what will change, confirms those changes worked, and closes the record with evidence. Every step is traceable, and every decision is accountable.
AQ’s CAPA management guide covers:
- What CAPA management is and why it matters in clinical research
- The full CAPA lifecycle: stage by stage
- Who does what across the CAPA process
- Root cause analysis methods used in clinical trials
- How CAPA connects to deviations, audits, QMS, and inspection readiness
- What CAPA management software does, and how to compare CAPA systems
- How AQ CAPA works and what makes it built for clinical operations
What Is CAPA Management?
CAPA stands for Corrective and Preventive Action. In clinical research, it is the formal process for identifying, investigating, resolving, and preventing recurrence of quality events: deviations, audit findings, document non-conformances, risk signals, and inspection observations.
Corrective action addresses what already happened. Preventive action changes the conditions that made the event possible. A CAPA record carries both, documented together, with evidence that each was executed and that the outcome was verified before the record closes. For the acronym itself and how the two halves differ in practice, see what CAPA stands for in clinical trial research.
In practice, CAPA management is the mechanism through which clinical research organisations demonstrate they can identify problems, understand them properly, resolve them systematically, and confirm the resolution held. Regulators do not expect perfection. They expect control and a functioning CAPA programme is evidence of it.
Clinical trials operate within tightly controlled environments where protocol deviations, data discrepancies, and procedural gaps carry direct consequences for participant safety, data integrity, and regulatory acceptance. CAPA management creates the operational structure required to identify issues, investigate root causes, implement corrective actions, and maintain long-term quality oversight across study operations.
MHRA inspection teams regularly assess CAPA programmes during sponsor and site audits. Well-documented CAPA records demonstrate operational control, accountability, and effective quality management. Repeated deviations without traceable resolution often signal deeper oversight failures.
ICH-GCP E6(R3) places clear expectations around quality issue management and effectiveness evaluation, which CAPA processes support through:
- Root cause identification and investigation
- Corrective action tracking with assigned ownership
- Preventive action implementation across future operations
- Effectiveness verification with supporting evidence
- Traceable documentation for audits and inspections
- Defensible quality oversight across sites, studies, and vendors
The CAPA Lifecycle: Stage by Stage
Every CAPA follows the same sequence. Each stage is a gate, not a label, and the record cannot advance until the stage before it is complete.
1. Initiation
The record opens when a quality event is identified, capturing the event, its source, its risk level and its owner. Source linkage is established here: the deviation or audit finding that prompted the CAPA and the CAPA itself each point at the other, so an inspector can navigate in either direction. Risk level sets the clock.
| Risk Level | Target Closure |
|---|---|
| Low | 90 days |
| Medium | 60 days |
| High | 30 days |
| Critical | 30 days: dual sign-off required |
2. Investigation
The investigator documents what was found, when, at which site, which records are implicated and what the impact on participant safety or data integrity was. Evidence is attached to the investigation record itself, timestamped and attributed, rather than emailed or filed separately. The record and its evidence are one unit.
3. Root Cause Analysis
The most consequential stage. A superficial analysis produces an action plan that treats the symptom, closes on time, and is followed by the same event six months later. Two structured methods are used: 5-Why, which repeats the question until the answer reveals a process or governance failure rather than an individual’s error, and Fishbone, which maps causes across six categories when several factors contribute at once.
The analyst then writes a root cause statement in plain language. It is the bridge between the analysis and the plan, and a reviewer should be able to read it and know exactly what has to change. Action planning does not open until the QA Lead approves it.
4. Action Planning
Each action carries a type, an owner and a due date on or before the target closure date. Actions must be proportionate to the cause. Responding to “no systematic review of training content after protocol amendments” with “retrain the coordinator” addresses the symptom; the preventive action has to introduce the missing review. Critical CAPAs need the QA Director to counter-sign before implementation begins.
5. Implementation
Owners execute their actions and attach evidence against the specific item, not as a general note on the record. An action marked complete with no evidence and no documented reason for its absence fails basic data integrity expectations. Overdue items are flagged automatically and escalate.
6. Effectiveness Verification
Completing the actions is not the same as resolving the problem. Criteria are set before verification begins and have to be measurable: “no further issues identified” is not a criterion; “zero consent timing deviations in the 60-day post-action review, with training completion confirmed for all site staff with consent responsibilities” is.
The verifier cannot be the CAPA owner. The system enforces that separation rather than leaving it to a reviewer to notice. Three outcomes are possible: pass advances to closure; fail reopens the record at investigation and counts separately in the repeat-finding rate; partial gives the QA Lead five business days to add actions or reclassify as a fail. A failed check is not a process failure. Quietly reclassifying one as a pass is. Setting criteria that survive scrutiny is covered in CAPA effectiveness verification.
7. Closure and Electronic Signature
The QA Lead writes a closure summary substantive enough that a reader who has never seen the record can follow the whole story, then signs. Signing requires re-authentication, and the system records the signer, role, UTC timestamp, meaning statement and an SHA-256 checksum of the record as signed. That checksum binds the signature to the record state, satisfying 21 CFR Part 11 §11.70. After closure no field can be modified, and only a QA Director can reopen the record, with a written justification and a full audit trail entry.
Who Does What?
CAPA is cross-functional, and the integrity of the outcome depends on each role completing its own step rather than absorbing another’s.

The QA Specialist runs the record day to day: raising it, investigating, building the analysis, defining actions and tracking implementation. The QA Lead is the gate at every stage that advances, approving the analysis and the plan, setting the verification criteria and signing closure. The QA Director counter-signs Critical CAPAs, holds the authority to reopen a closed record, and answers for programme health to sponsors and regulators.
Around them, action owners execute and evidence their own items, site staff are usually where the event surfaced and often where the fix lands, sponsors take programme-level visibility as part of oversight, and regulatory affairs draw on closed records when building inspection responses.
CAPA and Root Cause Analysis in Clinical Trials
Root cause analysis in clinical research carries specific operational constraints that generic RCA frameworks do not account for.
Clinical trials run across multiple sites with different staffing, training levels, and local procedures. A root cause identified at one site may reflect a systemic issue across all sites, or may be site-specific. The RCA needs to be sensitive to this distinction, an action plan calibrated to one site’s practice gap will fail effectiveness verification if the underlying cause is a protocol-level ambiguity affecting all sites.
Clinical trials also operate under protocol constraints. Some findings reflect protocol design issues rather than operational failures. A consent window that is operationally difficult to achieve generates deviations at every site. A root cause analysis that attributes repeated consent deviations to “coordinator error” when the protocol window is genuinely unworkable produces action plans that train coordinators to perform an impossible task, and fail effectiveness checks repeatedly.
The most important discipline in clinical trial RCA is separating the stated cause from the structural cause. A delegation log gap is stated as “coordinator failed to update the log.” The structural cause may be that the delegation log lives in a separate system from the visit schedule, nobody owns the task of updating it after each visit, and there is no automated prompt when a new activity is performed. Correcting the individual log entry without addressing the structural cause leaves the same gap open for the next visit.
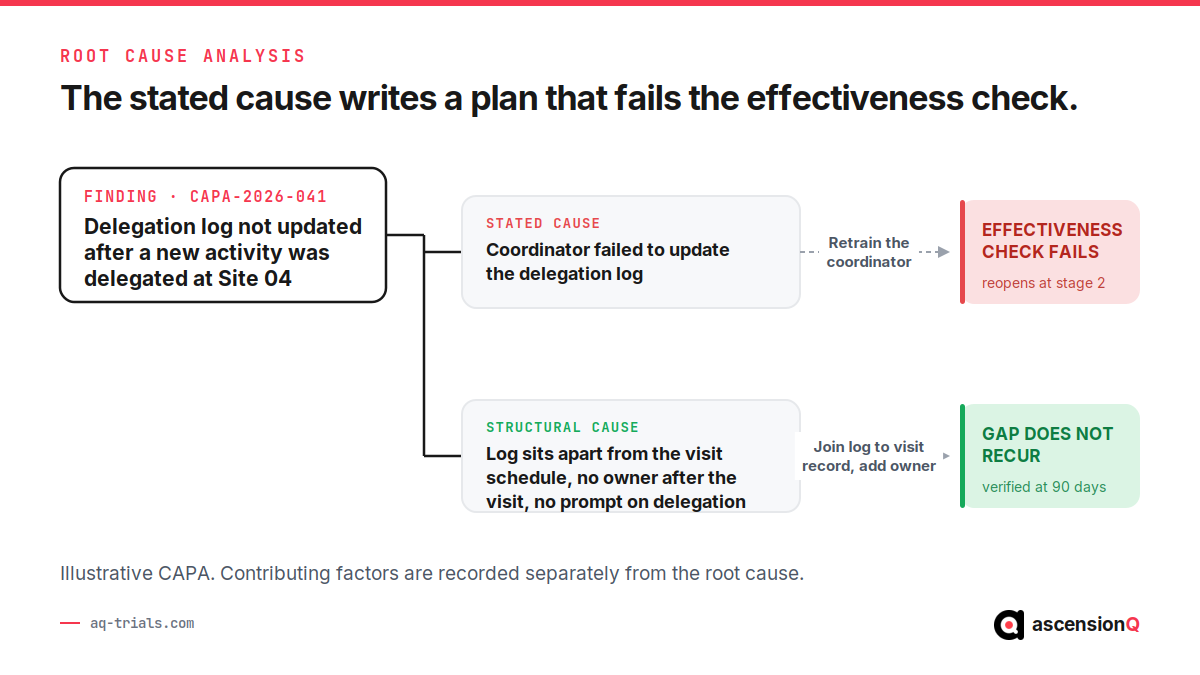
Contributing factors matter separately from the root cause. A staff change, a site recruitment peak, a technology limitation, an SOP that has not been reviewed since the protocol amendment, each may be a contributing factor rather than the primary cause. Preventive actions targeted at contributing factors reduce the risk of recurrence even when the root cause is addressed, because contributing factors lower the threshold for the same type of failure.
Turning a root cause statement into actions that hold is a separate discipline. Read how to build a CAPA action plan that addresses root cause for the containment, corrective and preventive layers and how each is calibrated. For the same reasoning applied end to end on one real finding, see this worked CAPA example of a clinical trial deviation.
How CAPA Connects to Deviations, Audits, and the QMS
CAPA management does not operate in isolation. In a structured quality programme, CAPA is the resolution layer that connects directly to the systems that identify quality events.
CAPA and Deviations
Protocol deviations are the most common source of CAPAs in clinical research. A Minor deviation may be managed and documented without a formal CAPA. A Major or Critical deviation should generate a CAPA, and the two records point at each other: the deviation shows which CAPA was raised, and the CAPA shows which deviation prompted it. An inspector can navigate in either direction and confirm the source was properly classified.
CAPA and Audit Findings
Audit findings, whether from internal QA, a sponsor or a regulatory inspection, generate CAPAs when the finding warrants formal action. The finding links to the CAPA, and the CAPA response forms part of the audit closeout evidence. Inspectors track findings across audit cycles, and an organisation that raises, completes, verifies and closes with evidence demonstrates findings are resolved rather than acknowledged.
CAPA and the QMS
The quality management system controls documents, SOPs, training and oversight. CAPA is its resolution component. Preventive actions frequently touch QMS elements: updating an SOP, adding a training module, creating a new oversight check. When a preventive action modifies a controlled document, that change belongs in the QMS document control workflow, not handled outside the system and referenced in the CAPA as “SOP updated.” In a connected programme the CAPA triggers the document change, and the updated document is the evidence in the CAPA record.
CAPA Management vs Spreadsheet-Based Tracking
Many clinical research organisations still manage CAPAs in spreadsheets. The operational and compliance limitations are structural, and they compound as the programme grows.
| Aspect | CAPA Management System | Spreadsheet Tracking |
|---|---|---|
| Lifecycle gates | System-enforced: stages open when their conditions are met | Manual: dependent on user discipline |
| Audit trail | Field-level, tamper-evident, automatic | None: version history at best |
| RCA tools | Structured 5-Why and Fishbone built into the record | Free text or attached document |
| Approval workflow | Routed automatically to the correct approver by role | Email-based, no enforcement |
| Electronic signatures | 21 CFR Part 11 aligned with re-authentication and record checksum | No signature capability |
| Overdue alerts | Automatic, escalating notifications | Manual calendar reminders |
| Programme metrics | Calculated automatically from live data | Manually compiled from individual records |
| Evidence management | Attached directly to action items, timestamped, locked | Separate folder, no attribution |
| Inspection readiness | Exportable complete record at any time | Manual compilation from multiple files |
| Scalability | Multi-study, multi-site, multi-CAPA without performance loss | Degrades rapidly with volume |
The compliance risk in a spreadsheet-based programme is cumulative. Each individual record may appear complete. The programme cannot demonstrate, across the full portfolio, that every CAPA was gated correctly, that every approval was obtained before implementation began, and that every closure was signed before the target date.
Moving off spreadsheets? See how AQ CAPA compares on the controls in the table above, before you shortlist.
CAPA in Inspection Scenarios: What Regulators Ask
MHRA inspectors, FDA investigators, and sponsor audit teams ask specific questions about CAPA programmes. The answers need to come from the system, not from the QA team’s recollection.

“Show me the CAPA raised for the consent deviation from the last monitoring visit.” The system navigates from the deviation to the linked CAPA, or the reverse. Both records display the reciprocal link, and the inspector verifies it without the QA team explaining it.
“Who approved this action plan and when?” The approval history shows the QA Lead approval with name, role and timestamp, plus the QA Director counter-signature on Critical CAPAs. Each approval event is recorded independently in the audit trail.
“Was the root cause analysis ever returned for revision?” The audit trail shows every submission, every return with the reviewer’s comment, and every resubmission. How the analysis developed is part of the record.
“How do you verify the corrective action was effective?” The verification plan shows criteria, method, scheduled date and assigned verifier. The outcome shows the observations and the evidence behind it. For a pass, why the team concluded the action worked. For a fail, that the record reopened.
“Can the person who owned the CAPA also verify its effectiveness?” The system blocks it. The inspector can confirm this is a system control rather than a convention.
“What is your on-time closure rate for the last 12 months?” The dashboard calculates it for any date range and exports a PDF stamped with the date, the filters applied and the calculation basis.
Inspection coming up? Ask us to walk one of your CAPA records through these six questions and see which of them your current process answers from the system.
What CAPA Management Software Does
CAPA management software holds the corrective and preventive action record for an organisation and enforces the sequence that record has to follow. A spreadsheet holds the same fields without enforcing anything. That difference is why the stage missing at inspection is almost always the stage nobody was prevented from skipping.
The category has a defined shape. A CAPA management system built for regulated research carries five functions, and a buyer can test each one in a demonstration.
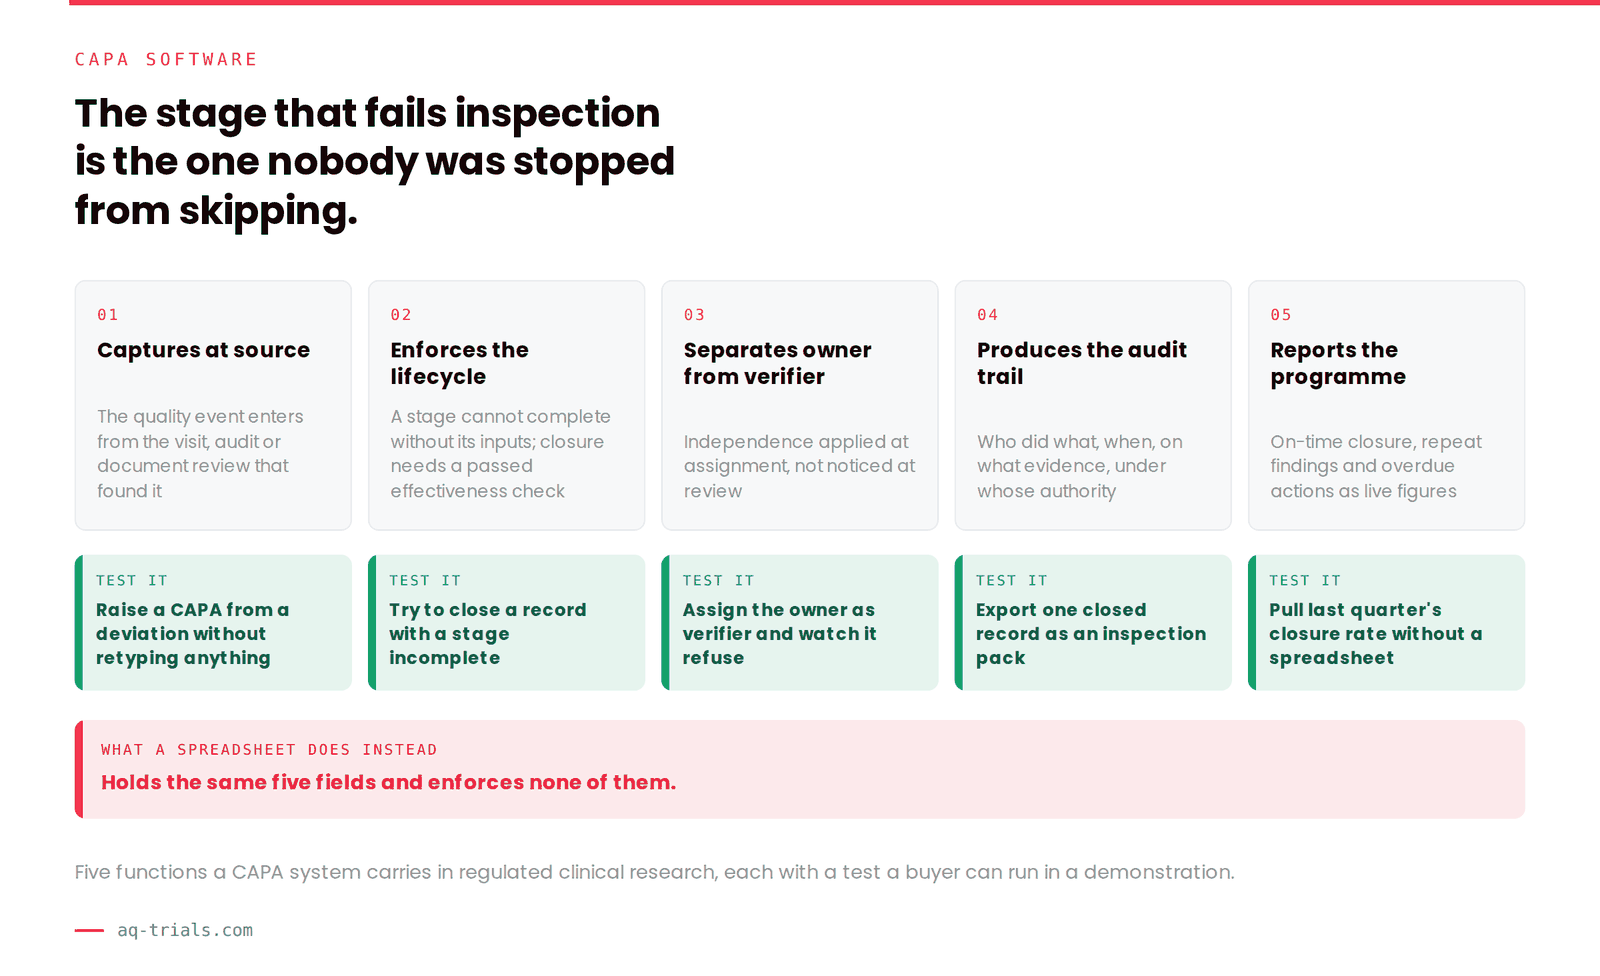
It captures the event where the event happens. A quality event starts in a monitoring visit, an audit, a deviation log or a document review. Software that sits apart from those workflows depends on somebody remembering to open a second system and re-enter what they already recorded. Capture at source carries the originating record with the CAPA, so the investigation starts with the evidence attached rather than referenced.
It enforces the lifecycle rather than describing it. Every organisation has the sequence written into an SOP. Software enforces it in the record: a stage cannot complete without its inputs, an action plan cannot be approved without a root cause statement, a record cannot close without a passed effectiveness check. The SOP stops being a document people are trained on and becomes the behaviour of the system.
It separates ownership from verification. Independence is a control, not an etiquette. The separation is applied at the point of assignment, rather than left for a reviewer to notice later that the same name appears twice.
It produces the CAPA audit trail on demand. An inspector expects to see who did what, when, on what evidence and under whose authority. A secure audit trail with attributable, time-stamped entries and controlled electronic signatures answers that in the system. Reconstructing it from email threads answers it slowly, and the delay is itself a finding. This is the function most often tested and most often weak.
It reports across the programme. One CAPA tells you about one event. On-time closure rate, repeat-finding rate, overdue count and average closure time tell you whether the quality system is working. Held as live data, they are current. Compiled by hand, they are quarterly at best, and the programme is assessed on a picture already months old.
General-purpose quality tools from manufacturing carry the lifecycle and stop there. Clinical research adds requirements they were never shaped around: alignment with ICH-GCP E6(R3) expectations for quality issue management and effectiveness evaluation, ALCOA+ attributes on every record, delegation and access that follow the study rather than the org chart, and retention that outlives the study by decades. Ask any vendor how their system handles a CAPA raised against a site that closed three years ago.
The second question is what the system connects to. A CAPA raised from a deviation, resolved through a document change and verified against a training record touches three systems in most organisations, and when those are separate the connections are maintained by people. Compare how CAPA is handled across platforms before shortlisting, and test the connection points rather than the feature list.
Still building your shortlist? See what AQ CAPA management software covers against the five functions above.
What Is the Best CAPA Software for Clinical Trials?
The best CAPA software for clinical trials is the system that matches where your quality events start and who has to answer for them. Sponsors and manufacturers with a quality remit wider than trials usually shortlist MasterControl, Qualio or Veeva. Research sites and UK trusts need the CAPA record beside the site file the finding came from.
Four systems come up most often on a clinical CAPA shortlist. Each row below paraphrases that vendor’s own product page, checked on 8 October 2026.
| System | How the vendor describes it | Capabilities the vendor publishes | Fits best | Hosting stated on the product page |
|---|---|---|---|---|
| MasterControl CAPA | A closed-loop solution for automating the CAPA process that connects quality channels across the product lifecycle | Automated routing, notifications, escalation and approvals. CAPA forms launched from complaints, deviations, nonconformances, audits and out-of-specification events. Change control and training verification triggered when connected to its wider quality suite. Data tracking and trending. No root cause method is named on the page. | Regulated manufacturers and life sciences organisations with FDA-facing quality programmes | Not stated |
| Qualio Events | CAPA and non-conformance management on one workflow-driven platform, from root cause to close-out | Configurable workflows and templates for non-conformances, deviations, incidents, near misses and complaints. Task routing and automatic reminders. Events linked to documents, training records, customers, tickets and equipment. Reports on incident rates, closed CAPAs and outstanding tasks. Effectiveness checks are not described on the page. | Life sciences companies that want quality events, documents and training on one platform | Not stated |
| Veeva Vault QMS | A cloud-based quality management system for life sciences quality processes | Deviations, complaints, audits, change control, supplier quality and quality risk management. Real-time access for external partners to investigations, audit findings and corrective actions. A connection to Veeva CTMS for study data and protocol deviation management. CAPA appears in the page metadata and the body text refers to corrective actions. Document control and training are separate Vault applications. | Sponsors and manufacturers running quality across a wide supplier and partner network | Cloud. Region not stated. |
| AQ CAPA | The issue resolution module of AQ Platform, built for clinical research operations | A gated lifecycle that locks each stage until its inputs are complete. 5-Why and Fishbone held as structured data in the record. Owner and verifier kept apart by the system. Re-authentication and a record checksum at closure. A continuous activity log. On-time closure, repeat-finding, overdue count and average closure time calculated from live data. | UK research sites, NHS trusts and sponsors that want the CAPA record on the same platform as the site file, the pharmacy file and the quality system | UK-hosted. NHS DSPT Standards Met (2026). Cyber Essentials certified. |
No system on this list is the only option, and the four are not shaped for the same buyer. MasterControl and Qualio answer a quality remit that runs well beyond trials, taking in supplier quality, complaints and post-market work that AQ does not cover. Veeva suits an organisation whose quality processes already sit in Vault. The dividing line for a research site is where the CAPA record lives. A sponsor-side quality platform receives site evidence after the event. A site-side record holds the deviation, the document change and the training record on the study that produced them.
In AQ CAPA, a record cannot close until an effectiveness check has passed, and the system blocks the person who owned the actions from verifying them.
What Is the Best CAPA Software for Clinical Research Sites in the UK?
A UK research site needs CAPA software that answers to UK rules: a 25-year retention duty, MHRA findings that arrive graded, serious breaches reported on a seven-day clock, and NHS information governance evidence before go-live. Sponsor-side quality platforms rarely carry the site file the finding came from.
Seven conditions separate a system that works for a UK site from one that works anywhere. A system built for another market can meet all seven. The buyer has to ask for the evidence.
| UK condition | Where it comes from | What to ask the supplier |
|---|---|---|
| Records kept for at least 25 years after the trial ends | The Medicines for Human Use (Clinical Trials) (Amendment) Regulations 2025 (SI 2025 No. 538), made 28 April 2025 and in force 28 April 2026, regulation 31A | How a closed CAPA record stays readable after the contract ends, and who holds it |
| Quality management proportionate to risk, with the causes of serious non-compliance identified and prevented | ICH E6(R3), adopted 6 January 2025 and applying in the UK from 28 April 2026, sections 3.10 and 3.11.1 | Whether root cause analysis is structured data the programme can be analysed across, or a free-text box |
| Deviations documented and recurrence prevented by the investigator | ICH E6(R3), section 2.5.3 | Whether a site can raise and close a CAPA in its own system without waiting for the sponsor’s |
| Quality measures reviewed for continued effectiveness | ICH E6(R3), section 3.10.1.5 | Whether effectiveness criteria are set before verification starts, and whether a failed check reopens the record |
| Serious breaches notified to the MHRA within seven days | Regulation 29A of the Medicines for Human Use (Clinical Trials) Regulations 2004, as amended. The duty sits with the sponsor, so a site has to escalate fast enough for the sponsor to meet it | Whether the record timestamps the moment the site became aware, and whether the escalation itself can be evidenced |
| Inspection findings graded critical, major or other, answered with a CAPA plan | MHRA good clinical practice inspection guidance on gov.uk | Whether one graded finding can link to several CAPA records and still report as one response |
| NHS information governance evidence before go-live | NHS Data Security and Protection Toolkit, Cyber Essentials and DTAC, verified by the trust | The supplier’s DSPT status and year, its Cyber Essentials certification, and where the data is hosted |
Two of these conditions decide most UK shortlists. The retention duty outlives the contract that bought the system, so a site needs to know what a CAPA record closed this year still looks like in 2051. The seven-day clock runs from the moment somebody at the site becomes aware of the breach, which makes the escalation route as important as the closure workflow.
AQ CAPA sits on the same platform as AQ eISF, AQ Pharmacy and AQ QMS, so a finding raised at a site, the document change that answers it and the training record behind it stay on one record.
Also read: CAPA Software for NHS Research: Deviations and MHRA Readiness for the trust-level view, and DSPT and Cyber Essentials: What NHS Procurement Expects of Research Software for the assurance pack a trust checks before go-live.
Frequently Asked Questions
What is CAPA management in clinical research?
CAPA management in clinical research is the formal process for identifying a quality event, investigating it, establishing its root cause, acting on that cause and confirming the action worked. Corrective action addresses what already happened. Preventive action changes the conditions that allowed it.
What is the best CAPA software for clinical trials?
The best CAPA software for clinical trials depends on the quality remit it has to cover. MasterControl, Qualio and Veeva Vault QMS are commonly shortlisted by sponsors and manufacturers whose quality system reaches well beyond trials. Research sites decide on where the CAPA record sits in relation to the site file and the training record that evidence it.
What is the best CAPA software for clinical research sites in the UK?
The best CAPA software for clinical research sites in the UK meets seven conditions: 25-year retention, risk-proportionate quality management under ICH E6(R3), site-level deviation handling, effectiveness review, an escalation route that lets the sponsor notify a serious breach within seven days, graded inspection findings answered with a CAPA plan, and DSPT, Cyber Essentials and DTAC evidence a trust can verify. AQ CAPA is UK-hosted and holds the CAPA record on the same platform as the site file and the quality system.
How long must CAPA records be kept in the UK?
Trial master file documents must be kept for at least 25 years after the trial ends under the UK Clinical Trials Regulations as amended, in force from 28 April 2026. Quality records that form part of that file follow the same period. A CAPA record closed today therefore has to stay readable long after the system holding it is replaced.
Can the person who owned a CAPA verify that it worked?
No. Independence of the effectiveness check is a control, and the verifier should never be the person who owned the actions. A system that applies the separation at the point of assignment gives an inspector something to confirm rather than a convention to take on trust.
Is CAPA software the same as a QMS?
No. A quality management system controls documents, SOPs, training and oversight, and CAPA is the resolution component inside it. Some vendors sell CAPA as a module of their quality management system. Others sell it as part of a wider clinical research platform.
Does a research site need CAPA software, or will a spreadsheet do?
A spreadsheet holds the same fields as a CAPA system and enforces none of them. A small site with a handful of quality events a year can keep a defensible spreadsheet record. The point a site outgrows it is usually the point it has to demonstrate, across a whole portfolio, that every CAPA was gated, approved and verified in the right order.
How AQ CAPA Works
AQ CAPA is the issue resolution module of the AQ clinical research platform. It answers the five functions above in the record itself rather than around it.
The lifecycle is gated, not labelled. Every record shows the full stepper, with future stages locked until their conditions are met. Root cause analysis is locked until the investigation is submitted, action planning until the analysis is approved, verification until implementation is complete. User discipline is not the control.
Root cause analysis is structured data. The 5-Why chain and the Fishbone diagram are built into the record rather than attached as a document, so the programme can be analysed across records. The Fishbone categories are clinical-specific (People, Process, Equipment and Technology, Environment, Measurement and Data, Materials and Documentation), where generic quality tools carry manufacturing categories that do not map to clinical research causes.
Independence and signature are enforced. The verifier cannot be the CAPA owner. Closure requires re-authentication and records the signer, role, UTC timestamp, meaning statement and an SHA-256 checksum of the record as signed, which cannot be detached or transferred.
Evidence and audit trail are continuous. Every field change, submission, approval, upload and transition is written to the activity log in real time. A closed record exports as a complete PDF (all stages, evidence, signatures and audit trail), suitable for an inspection response without manual compilation.
The programme reports itself. On-time closure rate, repeat-finding rate, overdue count and average closure time are calculated from live data and filterable by risk, status, source and date, with a stamped PDF export.
Connected to the rest of the record
CAPAs raised from deviations in AQ CTMS carry their source linkage automatically. Document non-conformances link to eISF or pharmacy site file records. Preventive actions that change a controlled document run through QMS workflows. Delegation gaps found through Digital DoA arrive with source attribution already attached.
The control chain (CTMS → eISF → Pharmacy → QMS → CAPA → Digital DoA) means an inspector following a thread from a site audit finding to the CAPA to the document change to the training record stays inside one system throughout. There is no point in the chain where a document lives elsewhere and its connection has to be explained rather than shown.
Summary
CAPA management in clinical research is the difference between a quality programme that records problems and one that resolves them. A well-structured process captures quality events at source, investigates them properly, defines actions that address root cause rather than symptom, confirms those actions were executed with evidence, and verifies the outcome before the record closes.
Regulators do not expect organisations to run perfect trials. They expect control: identify what went wrong, understand why, fix it properly, and demonstrate that the fix held. A functioning CAPA programme is the evidence of that control.
AQ CAPA management software gives quality teams the infrastructure to run that programme: gated lifecycle enforcement, built-in RCA tools, role-based approval routing, implementation tracking, independence-enforced verification and 21 CFR Part 11 aligned closure, connected to the full AQ platform so every quality event traces back to its source.
Book a live demo to see AQ CAPA run a full lifecycle: structured root cause analysis, role-based approval routing, implementation tracking, and independence-enforced verification before the record closes.
