
Objective response rate (ORR) is the proportion of participants whose tumour shrank by a predefined amount. It is the sum of complete responses and partial responses, divided by the number of evaluable participants. Stable disease is excluded.
ORR answers one question, at one point in time: did the treatment produce measurable tumour shrinkage in this person. It does not describe how long the shrinkage lasted, and it does not describe whether anyone lived longer. Those are separate endpoints, and conflating them is the most common error in reading an oncology result.
How ORR Is Calculated
The formula is simple. The definitions underneath it are not.
ORR (%) = (complete responses + partial responses) ÷ evaluable participants × 100
Two decisions drive the number. The first is what counts as a response, which comes from the response criteria named in the protocol. The second is who counts as evaluable, which comes from the analysis population the statistical analysis plan defines. A trial that reports ORR against participants who completed at least one post-baseline scan will produce a higher figure than one reporting against everyone who received a dose. Both are defensible. They are not comparable.
What Counts as a Response: RECIST 1.1
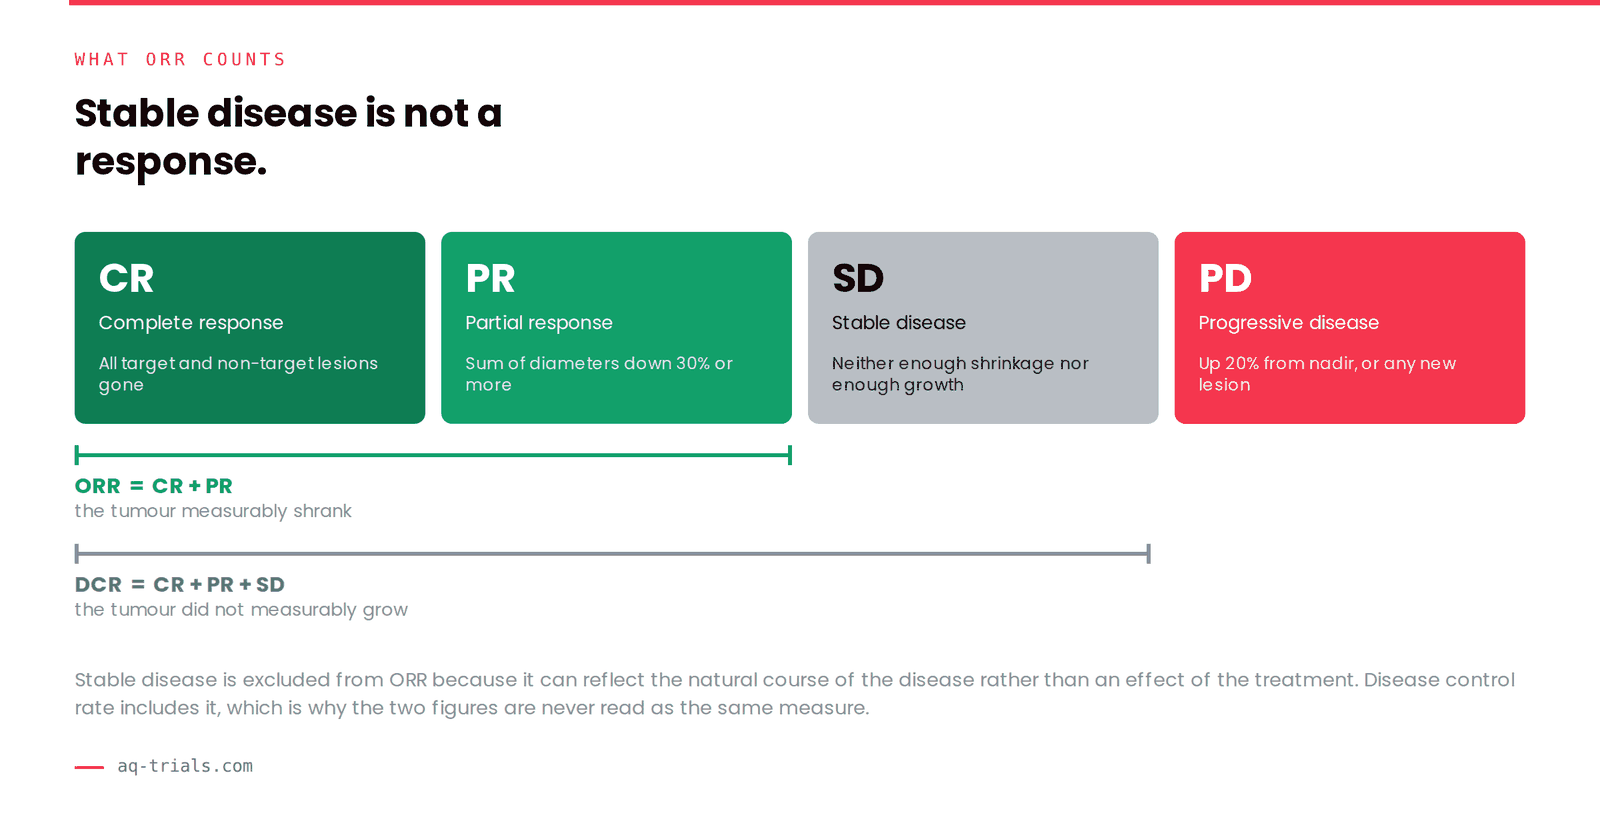
Most solid tumour trials assess response using RECIST 1.1 (Response Evaluation Criteria in Solid Tumours). The criteria turn a radiologist’s reading into one of four categories, and only two of them count toward ORR.
At baseline, the radiologist selects target lesions: up to five in total, no more than two per organ, each measuring at least 10 mm in longest diameter on CT. Lymph nodes are measured on their short axis and qualify as target lesions only above 15 mm. The longest diameters are added together to give the baseline sum of diameters, and every later assessment is compared against it.
| Category | RECIST 1.1 threshold | Counts toward ORR |
|---|---|---|
| Complete response (CR) | Disappearance of all target and non-target lesions | Yes |
| Partial response (PR) | At least a 30% decrease in the sum of diameters from baseline | Yes |
| Stable disease (SD) | Neither enough shrinkage for PR nor enough growth for PD | No |
| Progressive disease (PD) | At least a 20% increase from the smallest recorded sum, with an absolute increase of at least 5 mm — or any new lesion | No |
The last clause matters more than its length suggests. Under RECIST 1.1, a single new lesion is progressive disease, whatever the target lesions are doing. A participant whose measured tumours shrank by 40% and who developed one new lesion has progressed, not responded.
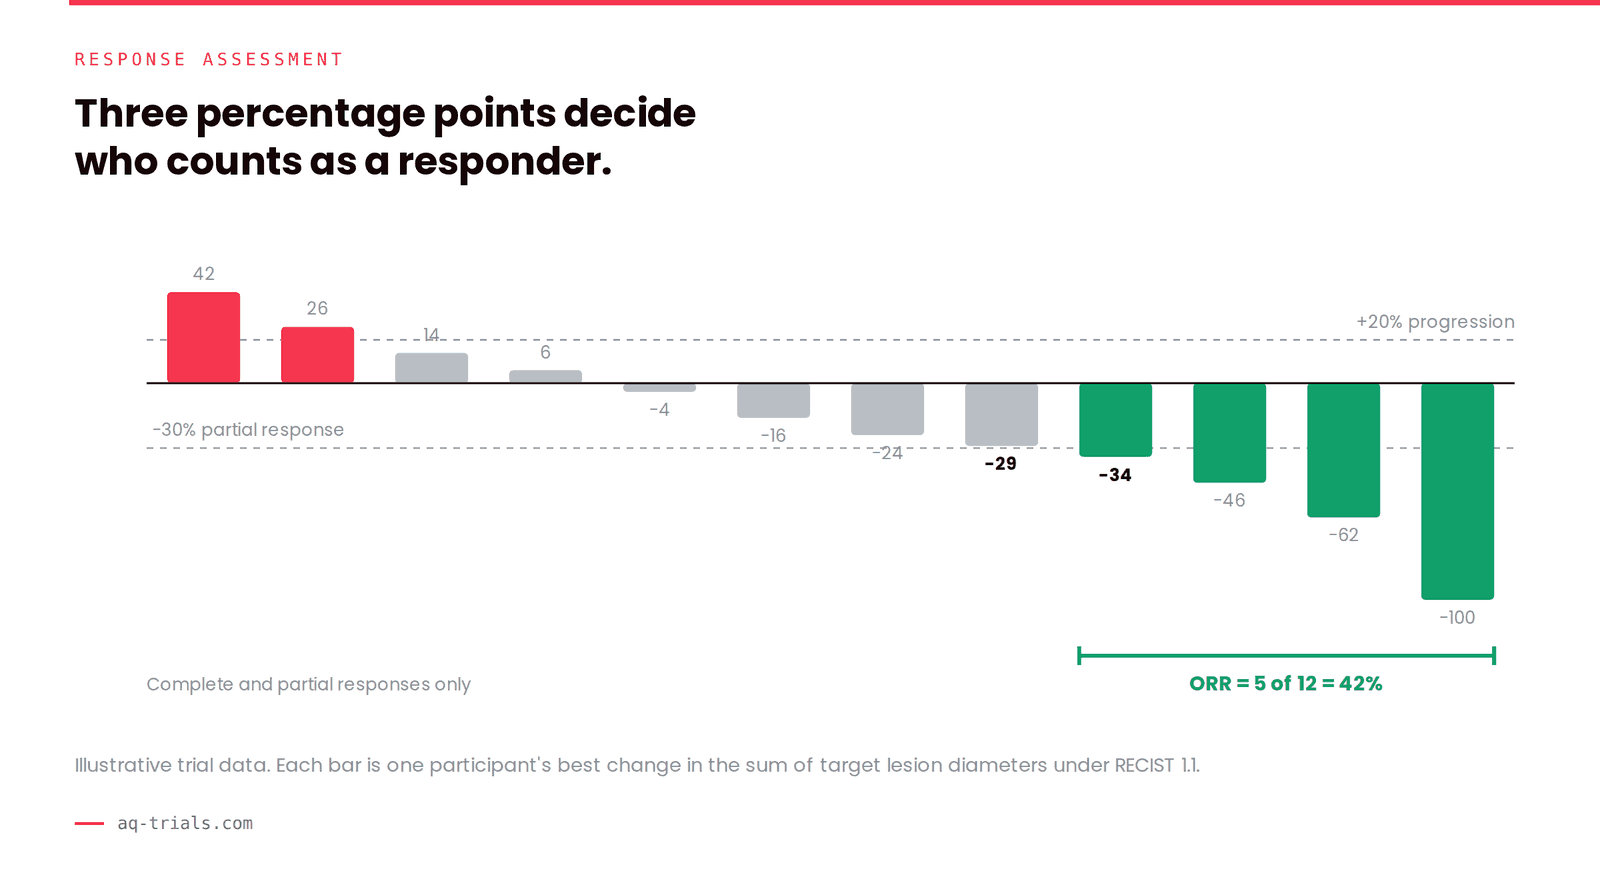
A waterfall plot of this kind is the standard way response data is presented, and it shows why the thresholds are doing the work. The bar at −29% and the bar at −34% describe two people whose tumours shrank by almost the same amount. One is a responder and one is not.
Best Overall Response and Confirmation
ORR is built from each participant’s best overall response: the most favourable category recorded across the whole assessment period, not the category at any single visit.
Many protocols require a response to be confirmed by a repeat assessment, typically no less than four weeks after the first. Confirmation exists because a single scan can be misread, and because measurement varies between readers and between machines. A trial reporting confirmed ORR and a trial reporting unconfirmed ORR are answering slightly different questions, and the confirmed figure is usually the lower of the two. Check which one a headline number refers to before comparing it with anything.
ORR Against DCR, DoR, PFS and OS
Oncology endpoints are frequently quoted side by side as though they were interchangeable. They measure different things over different spans of time.
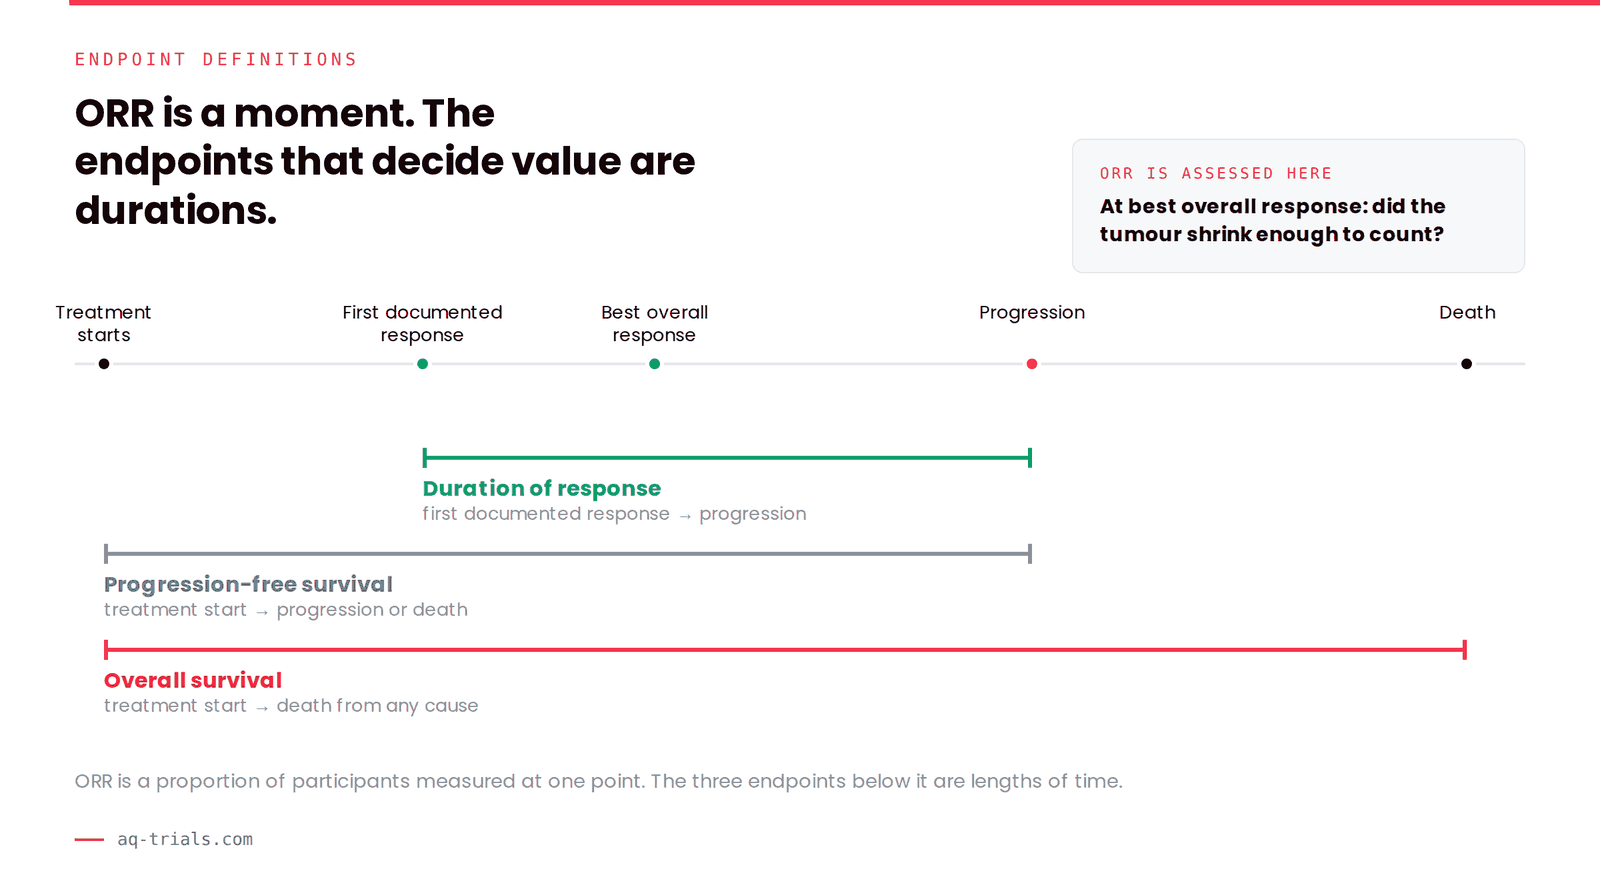
- Disease control rate (DCR) adds stable disease to ORR. It will always be the larger number, and it says something weaker: the tumour did not measurably grow.
- Duration of response (DoR) measures how long a response lasted, from first documented response to progression. ORR without DoR describes shrinkage of unknown durability.
- Progression-free survival (PFS) runs from treatment start to progression or death, and captures stable disease as benefit in a way ORR does not.
- Overall survival (OS) runs to death from any cause. It is the endpoint that matters most to participants and the slowest and most expensive to reach.
The FDA is explicit that stable disease should not form part of ORR, on the grounds that it may reflect the natural history of the disease rather than an effect of the drug. That single exclusion is what gives ORR its interpretive value: a tumour that shrinks by a third is doing something it would not otherwise have done.
Why Regulators Accept ORR
ORR reads out early, needs fewer participants than a survival endpoint, and can be attributed to the drug rather than to the natural course of disease. Those three properties make it the working endpoint of early-phase oncology and the basis of many accelerated approvals.
The FDA has accepted ORR together with duration of response from single-arm studies as evidence supporting accelerated approval, particularly where no alternative therapy exists and the tumour regressions are large enough to attribute to the drug. The significance of an ORR result is judged on three things together: its magnitude, its duration, and the proportion of responses that were complete. A 45% ORR made up largely of brief partial responses is a different result from a 30% ORR with durable complete responses, even though the first number is larger.
Where ORR Misleads
ORR has four well-documented limitations, and the FDA names most of them in its own endpoint guidance.
It may not correlate with survival. Tumour shrinkage is a surrogate. Drugs have produced strong response rates without extending life, which is why accelerated approvals carry confirmatory trial obligations.
Definitions vary between studies. Different response criteria, different evaluable populations, different confirmation requirements. Two ORR figures from two protocols are rarely measuring the same thing.
It depends on frequent imaging. The endpoint exists only because scans happen on schedule. Assessment intervals differ between trials, and a longer interval changes what the data can show.
It says nothing about duration. A response that lasts three weeks and one that lasts three years count identically toward ORR.
Immunotherapy and iRECIST
Immunotherapies produce response patterns that RECIST 1.1 was not built for. Tumours can appear to grow before they shrink, as immune cells infiltrate the lesion — pseudoprogression. Under RECIST 1.1 that reading is progressive disease, and treatment stops.
iRECIST was developed to handle this. It introduces iUPD (unconfirmed progression), which does not end assessment: a clinically stable participant continues treatment, and progression must be confirmed by a repeat scan four to eight weeks later before it becomes iCPD (confirmed progression). New lesions are measured and tracked separately rather than automatically ending the assessment, so a participant whose new lesions later stabilise or shrink can still be recorded as responding.
For anyone reading a result, the operative point is that an ORR figure derived under iRECIST is not directly comparable with one derived under RECIST 1.1.
What ORR Asks of Trial Operations
ORR is an imaging endpoint, which means it is produced by scheduling, documentation and oversight rather than by analysis alone. Four operational conditions determine whether the number is defensible at inspection.
Assessments happen inside the protocol window. Response is measured against a schedule. A scan performed outside its window produces a data point the analysis has to explain or exclude, and enough of them compromise the endpoint. A visit diary that applies the protocol window at the point of booking prevents the deviation instead of surfacing it at monitoring.
The reader is qualified and the qualification is evidenced. Response assessment is a delegated activity. The delegation log has to show that the person who read the scan was authorised to do so on the date they did it, which is a question about delegation of authority records rather than about radiology.
Baseline and follow-up measurements are traceable to source. The sum of diameters is a derived value. Every measurement behind it needs an attributable, time-stamped source record, and the derivation needs to be reproducible from that source years later.
Deviations against the assessment schedule are resolved, not just logged. A pattern of out-of-window scans at one site is a quality signal. Recording it closes nothing. Investigating the cause and confirming the fix held is what a CAPA process exists to do.
A clinical trial management system holds the visit schedule, the site activity and the deviation record that these four conditions depend on. AQ CTMS applies the protocol window at the point a visit is booked, so an assessment that would fall outside it is flagged before it happens rather than found afterwards.
Book a live demo to see how AQ handles protocol visit windows, delegation currency and deviation-to-CAPA traceability across a multi-site study.
