
The hospital pharmacy stock system is not a trial record, because it was built to control the trust’s medicines inventory and a trial record has to prove what happened to one numbered unit of investigational medicinal product for one named participant. The stock system counts product lines. Good clinical practice counts units against participants. A site treating the stock system as its accountability record holds the right medicine and the wrong evidence.
This guide covers what a stock system does well, what IMP accountability obliges the trial record to evidence, the two gaps that decide the question, and how a pharmacy holds both systems without drift.
- A stock system’s unit of record is the product line. The trial record’s unit is the individually numbered kit.
- ICH E6(R3) section 2.10.4 requires use by each participant, recorded with the code numbers of product and participant.
- The MHRA treats an audit trail as metadata about creating, changing or deleting a record. A stock adjustment carries no reason for change.
What Does a Hospital Pharmacy Stock System Do?
A hospital pharmacy stock system controls the movement and value of medicines through a department. It answers questions about supply, cost and expiry across the trust formulary, and it answers them well. The functions below are ones a trial pharmacy relies on daily.
- Stock holdings by product code. The system totals quantity by product and pack size, which gives the department a dependable picture of what it can supply.
- Goods-in against an order. Receipt posts against a purchase order or delivery note, which supports financial reconciliation and supplier queries.
- Batch and expiry at line level. The line holds a batch and the shortest expiry, which drives recall action and expiry rotation.
- Dispensing against a clinical prescription. An issue links to a patient and a prescriber, which supports the patient’s own medication record.
These are controlled records, kept to a professional standard. Descriptor 4.3 of the Professional Standards for Hospital Pharmacy Services covers the governance of all medicines, including investigational medicinal products, and descriptor 5.3 asks that clinical trial medicines are used in line with regulatory requirements. The question is which requirement each of those records can evidence.
What Must the Trial Record Evidence?
The trial record must evidence the full life of every unit of IMP at the site, unit by unit, in a form a third party can verify years later. Four sources set that expectation. The complete guide to IMP accountability for UK pharmacy teams sets out the record as a whole.
| Source | What it requires | What the record must carry |
|---|---|---|
| ICH E6(R3) 2.10.4 | Records of delivery, site inventory, use by each participant, and return or alternative disposition | Dates, quantities, batch numbers, expiry dates and the code numbers of product and participant |
| UK Clinical Trials Regulations 2004, Schedule 1 Part 2 paragraph 10 | Trial information recorded, handled and stored so it can be accurately reported, interpreted and verified | A record another party can reconstruct without its author present |
| MHRA GXP data integrity guidance 6.2 and 6.13 | Raw data as the first capture of information, and an audit trail as metadata about creation, modification or deletion | The original entry, every later change, and the who, when and why of each |
| ICH E6(R3) Annex 1, 4.2.2 and 4.3 | Relevant metadata including audit trails, with proportionate validation, security and training | Evidence the system was fit for the trial use it was put to |
Two words in that table decide the question. The first is participant. The second is why. A system holding neither is a supply tool rather than an accountability record.
Where Does the Stock System Fall Short of the Trial Record?
The stock system falls short at the level of the individual unit and at the level of the reason for a change. The table compares the two records on the attributes an inspector tests. It describes the general design of a trust stock system, so a site should confirm each row against its own configuration.
| Attribute | Trust pharmacy stock system | Trial accountability record |
|---|---|---|
| Unit of record | A product line with a quantity | One numbered kit, bottle or pack |
| Identity of the unit | Product code, batch, pack size | Kit number linked to the sponsor’s randomisation |
| Participant link | Patient and clinical prescription | Participant code, visit, trial prescription and allocated kit |
| Authority to act | Dispensary role permissions | The study delegation log and current study training |
| Reason for a change | An operational adjustment code | The trial event that caused it, recorded contemporaneously |
| Reconciles against | Physical count and purchase ledger | Sponsor shipments, allocations, prescriptions, returns, the shelf |
| Retention horizon | The department’s operational cycle | The statutory retention period for trial records, measured in decades |
Every row describes a design decision rather than a defect. The stock system was scoped before the trial existed, and the trial asks a narrower question about a smaller number of units. That narrower service is described in the guide to how a clinical trial pharmacy differs from routine dispensing.
Also Read: Paper Accountability Logs vs an Electronic Pharmacy Record
Why Is the Per-Participant Line the Gap That Matters Most?
The per-participant line matters most because it is the smallest reconcilable unit. A quantity against a product code has nothing to test it against. A kit number against a participant code is testable against the sponsor’s allocation, the trial prescription, the dosing record and the returns count.
A hypothetical delivery shows the difference in resolution. Twenty-four packs arrive at Northgate General for study NGH-017 at SITE 01. The stock system records one line: one product code, quantity 24, one location, one batch, one expiry. The trial record opens twenty-four lines, one per kit number, each with its own running status.
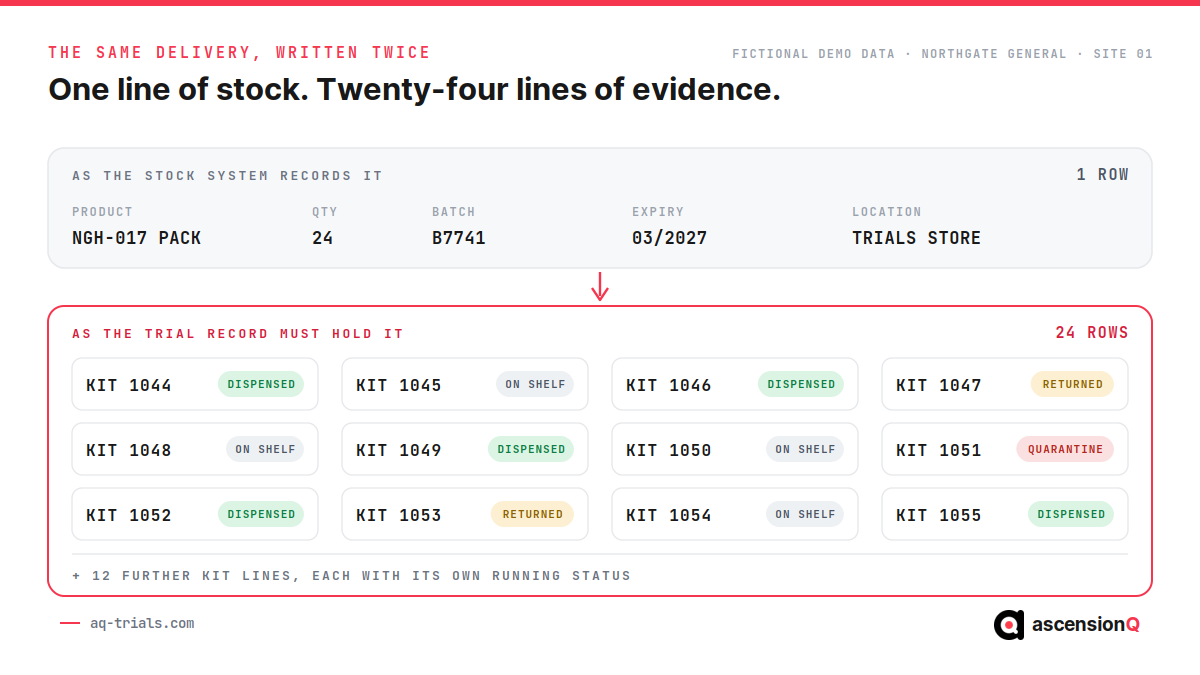
At visit 4, kit 1047 is dispensed to participant 017-012. The stock system can show that a pack of the study product left the dispensary against that patient. Three facts sit outside it. Kit 1047 was the kit the sponsor’s system allocated for that visit. Kit 1047 is the kit six unused tablets came back from at visit 5. Kit 1047 carries the batch a later temperature excursion placed under investigation.
A product line cannot be reconciled. A numbered unit can.
The allocation itself belongs to the sponsor, and the site ledger reconciles against it rather than replacing it. That boundary, and the four points where a value crosses it, is set out in which record an RTSM holds and which the pharmacy holds.
What Is Missing from the Audit Trail?
The reason for a change is missing. MHRA GXP data integrity guidance section 6.13 defines the audit trail as “a form of metadata containing information associated with actions that relate to the creation, modification or deletion of GXP records”. A stock system logs the action and the operator. It carries an operational adjustment code in place of the trial event that prompted the entry, and that code cannot be verified against the study.

Four consequences follow for a site relying on the stock audit trail alone.
- A correction cannot be tested. An adjustment with no recorded reason leaves a monitor unable to tell a trial event from a counting error.
- Attributability breaks at the login. An entry against a shared dispensary account does not show the person who acted was authorised for that study, and the tiers of authority appear in the guide to who is accountable for IMP at a trial site.
- The original entry can be overwritten. Section 6.2 treats raw data as the first capture of information, so a corrected balance that replaces the first figure has removed the raw data.
- Verification depends on export. A record that cannot leave the system with its metadata intact cannot be read independently.
The format of the record does not settle this. Section 3.7 of the same guidance states that moving between automated and paper systems “will not in itself remove the need for appropriate data integrity controls”. A paper log with a defensible correction convention holds a stronger audit trail than an electronic system that overwrites.
Which Records Can the Stock System Still Support?
The stock system remains a strong corroborating source. A monitor who finds two independent records agreeing on a date or a batch has stronger evidence than a single record asserting it. Four uses stand out.
- Goods-in date and quantity. The posted receipt gives a second, independently timed record of arrival, which supports the pharmacy entry if a delivery date is questioned.
- Batch and expiry. The line-level values cross-check what was transcribed into the accountability log, which catches a transcription error at the point it is made.
- Controlled drugs balances. A trial product that is a controlled drug stays in the register, which keeps that separate legal duty intact alongside the trial record.
- Location and storage assignment. The store location ties a unit to the equipment whose temperature and calibration records cover it, and those records are set out in the investigational product storage records checklist.
Corroboration has one condition. The pharmacy file states which system holds the source record for each fact, so a later reader knows which figure governs.
How Should a Site Hold Both Systems Without Drift?
A site holds both systems by naming one source record per fact and making the trial entry part of the action rather than a later transcription. Five controls carry that.

- Name the source record. The pharmacy file states which system governs each fact, which settles the question at the moment two figures differ. The section index that holds it appears in what belongs in a pharmacy site file.
- Segregate and flag trial stock. Trial product sits in its own location and carries a flag in the stock system, which stops routine dispensing drawing a participant’s unit.
- Write the accountability entry at the bench. The kit-level entry forms part of the dispensing step, which keeps it contemporaneous and closes the transcription gap.
- Reconcile the two at a stated frequency. A scheduled comparison of the stock position against the accountability balance surfaces a difference while its cause is traceable.
- Write the boundary into the SOP. The pharmacy manual and the site procedure both state the rule, so a new starter inherits it.
Inspection tests the result rather than the intention, and the findings that follow a record set failing that test are covered in the guide to common MHRA GCP inspection findings.
Also Read: RTSM and IRT vs the Pharmacy Record: Which Holds What?
What Trial Software Integrates With Our Pharmacy System?
Most trial software does not integrate with a trust pharmacy stock system, and most sites do not need it to. The two records answer different questions, so they are held in parallel and reconciled on a stated frequency. Ask a supplier what it reconciles, what it claims to connect, and for the evidence behind each answer.
The obstacle is ownership rather than technology. A trust stock system is scoped for the whole formulary, sits inside the trust network, and is changed through the trust digital team on its own release cycle. A trial platform is procured for research and holds data the stock system was never designed to carry. The word integration covers several different things in that setting, and they are worth separating before a procurement conversation.
| What people mean by integrate | What it looks like in practice | What to ask the supplier |
|---|---|---|
| Goods-in data flowing across | Receipts posted in the stock system are carried into the trial record as a scheduled or manual file | Who owns the file, how often it runs, and what happens the week it fails |
| Scanning at the bench | The kit number is captured into the trial record at the moment of dispensing | Whether the scan writes to the trial record, the stock system or both |
| Participant and prescription data | Rarely available, because the trial prescription and the participant code do not exist in the stock system | Whether the supplier means the trust patient record or the trial record |
| Single sign-on from trust identity | Staff reach the trial record with their trust credentials rather than a separate login | Whether it is live today, with which identity provider, and who in the trust approves it |
| Reconciliation reporting | The stock position and the accountability balance are compared on a schedule, with differences explained in one place | What the report shows, who signs it, and where the signed copy is filed |
Only the last row changes the inspection position. An interface moves data faster. Reconciliation is what evidences that the two records agree, and it is the control an inspector can test. A site with no interface and a signed monthly reconciliation is in a stronger position than a site with a nightly feed nobody reviews.
Two further points are worth settling in the same conversation. An interface between two systems is itself a computerised system and carries its own validation evidence under ICH E6(R3) Annex 1. The source record rule still has to be written down, because a feed does not decide which figure governs when the two disagree.
AQ Pharmacy holds the kit-level accountability record alongside the storage history and the rest of the pharmacy site file, so a site reconciling against the stock system compares one balance rather than assembling several first.
Reconciliation is the control. An interface is a convenience.
Frequently Asked Questions
Why is the hospital pharmacy stock system not a trial record?
It was built to control the trust’s medicines inventory. A trial record has to prove what happened to one numbered unit of IMP for one named participant.
Where does the stock system fall short of the trial record?
At the level of the individual unit and at the level of the reason for a change. The per-participant line is the gap that matters most, because it is the smallest unit that can be reconciled.
How does a site run both systems without them drifting apart?
By naming one source record per fact and making the trial entry part of the action rather than a later transcription. The stock system then remains a useful corroborating source.
What trial software integrates with our pharmacy system?
Very little of it integrates with a trust stock system, and a site rarely needs that. The stock system and the trial accountability record hold different units of record, so they are kept in parallel and reconciled on a stated frequency. Ask any supplier to separate what it reconciles from what it claims to connect, and to say which connections are live today rather than planned.
Who decides which system holds the source record for a fact?
The site decides and writes it into the pharmacy file and the SOP, usually with the sponsor’s agreement. Unit and participant facts belong to the trial record. Departmental supply and cost facts belong to the stock system. The rule matters most at the moment two figures differ.
Does the hospital stock system still have a role in the trial?
Yes, as a corroborating source. Goods-in dates, batch and expiry values, controlled drug balances and storage location all gain strength from a second independent record. A monitor who finds two systems agreeing on a date has better evidence than one system asserting it.
Pharmacy records hold their value alongside the rest of a study’s evidence rather than in a system built for a different purpose. AQ’s electronic pharmacy site file page sets out how AQ approaches pharmacy documentation as part of one connected site record. Book a live demo to talk through where your pharmacy records and your study record meet today.
