
The amended UK Clinical Trials Regulations took full effect on 28 April 2026, and ICH-GCP E6(R3) came into force in the UK on the same day. Between them they place four testable demands on the software an NHS organisation uses to run research: the system has to hold a registration date, produce a results record inside a fixed period, evidence that it is fit for purpose, and keep essential records readable for at least 25 years.
Published guidance describes these as duties for sponsors and investigators. Inside a trust, each duty resolves into a single record with a date on it, held in a system that either produces that record on request or leaves someone to reconstruct it. That is the practical question facing NHS hospital research teams in 2026: which of the new obligations does the current software estate actually evidence?
This guide covers:
- The four provisions that now bind research software in the UK, and what each one binds.
- The statutory clocks introduced on 28 April 2026, with the event that starts each one.
- What ICH-GCP E6(R3) Principle 9 and Annex 1 Section 4 require of a computerised system.
- Where the evidence chain breaks inside a typical NHS software estate.
- The 25-year retention duty under regulation 31A and the contract questions it raises.
What Changed for NHS Research Software on 28 April 2026?
The Medicines for Human Use (Clinical Trials) (Amendment) Regulations 2025 (SI 2025/538) took full effect on 28 April 2026. The MHRA applies them on a binary basis: applications submitted before that date run under the former requirements as “old rules” trials, and everything submitted from that date runs under the amended regulations. A trust therefore operates two regulatory populations at once, and the systems have to tell them apart.
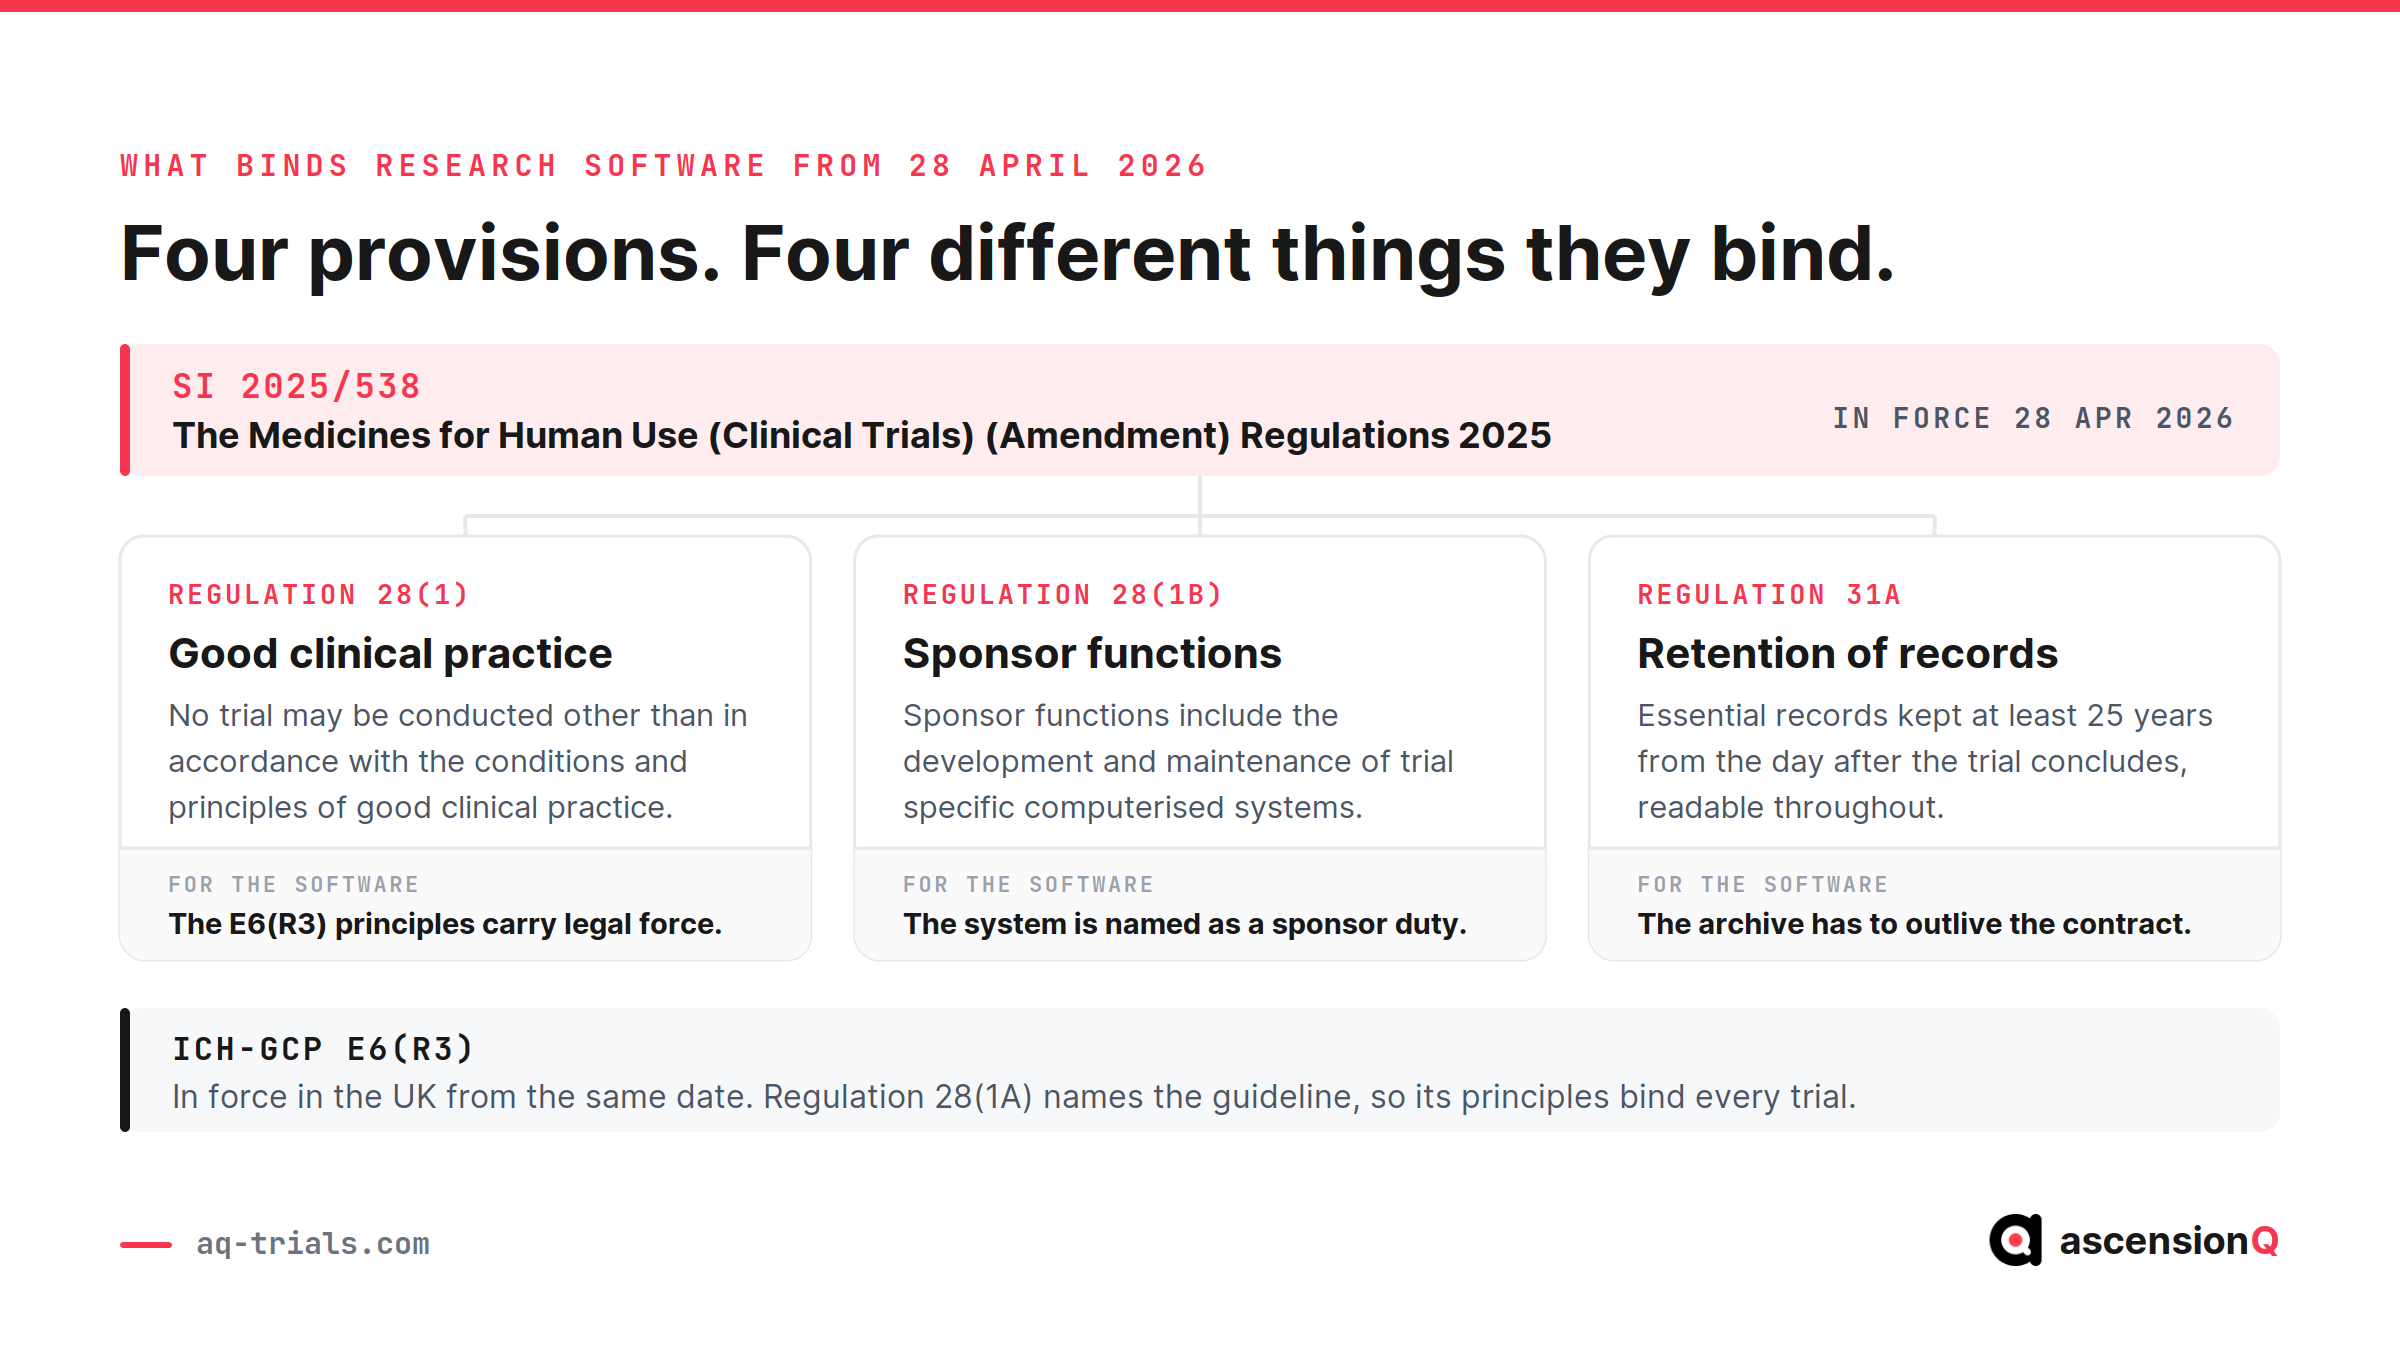
Four provisions now sit behind a research software decision. They bind different things, and confusing them is what produces a specification that misses the point.
- SI 2025/538 makes registration of a trial and publication of summary results a legal requirement for the first time, and introduces the notification scheme for lower-risk trials.
- Regulation 28(1) of the 2004 Regulations states that no person shall conduct a clinical trial otherwise than in accordance with the conditions and principles of good clinical practice, and regulation 28(1A) confirms that those conditions and principles include the ICH Guideline for Good Clinical Practice as amended from time to time. The principles of ICH-GCP E6(R3) carry legal force through this route.
- Regulation 28(1B) states, for the avoidance of doubt, that the functions of the sponsor include functions in relation to the development and maintenance of trial specific computerised systems. Responsibility for the system sits with the sponsor by name.
- Regulation 31A sets the retention duty: essential records held for at least 25 years, readable and available to an inspector throughout.
The MHRA has been explicit that ICH-GCP E6(R3) came into force in the UK alongside the updated regulations, that all trials must adhere to the principles of GCP, and that trials supporting a marketing authorisation must comply with the full guideline. Organisations claiming ICH E6 compliance are held to the annexes as well. The full walk-through of what sites and sponsors must do sits in our guide to the new UK Clinical Trials Regulations. This guide takes the next step and asks what those duties require of the software.
The duty belongs to the sponsor. The proof belongs to a system.
Which Duties Now Carry a Statutory Clock?
Several obligations that used to rest on good practice now run against a published deadline, and a missed deadline is an offence rather than an observation. The MHRA has confirmed it may use infringement notices and prosecution where transparency duties are breached. Each clock below starts from an operational event, which means the system holding that event has become the system of record for a legal duty.
| Duty | The clock | Event that starts it | Record that proves it |
| Register the trial in a public registry | Before first consent, or within 90 days of approval, whichever comes first | Approval to start, or first participant consent | Dated registry entry with the registration identifier |
| Register a trial already running on 28 April 2026 | By 27 July 2026, or before first consent if earlier | Transitional arrangements | Dated registry entry against the existing study record |
| Publish a summary of results | Within 12 months | Global end of trial | Dated posting in the same registry |
| Offer a lay summary to relevant persons (trials submitted from 28 April 2026) | Within 12 months | Global end of trial | Record of the offer and how it was made |
| Retain essential records | At least 25 years | The day after the conclusion of the trial | Archive index, readable copy, access log |
| Name an individual responsible for archiving | Continuous | MHRA archiving guidance | Current record naming the appointed custodian |
The lay summary duty applies to trials submitted from 28 April 2026. The HRA encourages sponsors of trials already underway on that date to offer one voluntarily. Every row otherwise reduces to a date and an owner. A trust that can produce both from one place has satisfied the evidential half of the duty. A trust that reconstructs either from correspondence has a gap that only appears when someone asks.
What Does ICH-GCP E6(R3) Require of a Computerised System?
E6(R3) replaced E6(R2) and restructured good clinical practice around 11 principles supported by annexes. Principle 9 is the one that reaches directly into software. It states that clinical trials should generate reliable results, and its six sub-principles describe the conditions under which a system can be relied on.
Principle 9: the six statements that bind a system
- 9.1 Fit for purpose information. The quality and amount of information generated should support confidence in the results, which sets the evidential bar the system has to clear.
- 9.2 Fit for purpose systems. Systems for data capture, management and analyses should capture the data the protocol requires and be implemented proportionately to risk, so the specification follows the protocol rather than the vendor feature list.
- 9.3 Risk-based validation. Computerised systems should be fit for purpose through risk-based validation where appropriate, which makes validation evidence a deliverable rather than an assurance.
- 9.4 Record integrity and traceability. Processes for managing records should maintain integrity and traceability and protect personal information, which is what allows accurate reporting and verification later.
- 9.5 Secure retention. Essential records should be retained securely by sponsors and investigators for the required period, which ties the guideline to regulation 31A and its 25 years.
- 9.6 Transparency. Transparency includes timely registration on recognised databases and public posting of results, which places the registry duties inside GCP as well as inside the regulations.
How Should Sites Apply ICH E6(R3) Data Governance to Their Systems?
Sites apply ICH E6(R3) data governance by naming every system that holds trial data, deciding who owns each record in it, and keeping the audit trail, corrections and access controls reviewable inside that system. Annex 1 Section 4 sets out the detail. The work starts with an inventory and a named owner for each system.
Annex 1 Section 4 covers data governance for the investigator and the sponsor, and it is the operational detail behind Principle 9. Section 4.2 walks the data life cycle. Section 4.3 addresses computerised systems directly. An NHS R&D office reading a vendor response should be able to point at each numbered item and find an answer.
- 4.2.2 Relevant metadata, including audit trails. The audit trail is part of the record, so an export that carries data without metadata does not carry the evidence.
- 4.2.3 Review of data and metadata. Someone reviews the audit trail, which requires the audit trail to be legible to a person rather than a database administrator.
- 4.2.4 Data corrections. Corrections carry a reason and an identity, which is the difference between a corrected record and an altered one.
- 4.2.5 Data transfer, exchange and migration. Migration is a validated activity with documentation, which becomes relevant every time a trust changes supplier.
- 4.2.7 Retention and access. Retention includes continuing access, so an archive that cannot be opened satisfies neither the annex nor regulation 31A.
- 4.3.3 Security and 4.3.8 user management. Access control is named at system level, which makes leaver and joiner processes part of GCP compliance.
- 4.3.4 Validation and 4.3.5 system release. Validation evidence and a controlled release path both belong to the sponsor’s file, not only to the vendor’s.
- 4.3.6 System failure and 4.3.7 technical support. A documented failure procedure decides what happens to trial conduct during an outage.
An inventory turns the annex into a list a site can work through. Most NHS sites hold trial data in six places, and each one answers to a different part of Section 4. The table below gives the starting inventory and the person who owns the record at site level.
| System at the site | What it holds | Section 4 items it has to satisfy | Who owns the record |
| CTMS or local portfolio system | Study list, approval and milestone dates, site status, regulatory population | 4.2.2 metadata, 4.2.7 retention and access | R&D office |
| Electronic data capture | Participant data and the queries raised against it | 4.2.2 metadata, 4.2.3 review, 4.2.4 corrections | Investigator, with the data manager |
| Investigator site file | Essential records held by the site | 4.2.7 retention and access, 4.3.3 security | Investigator |
| Trial master file | Sponsor-held essential records | 4.2.5 transfer and migration, 4.2.7 retention | Sponsor, with the site for site-held copies |
| Quality system and training records | SOPs, CVs, GCP and protocol training, delegation entries | 4.3.4 validation, 4.3.8 user management | R&D quality lead |
| Pharmacy site file and accountability record | IMP receipt, storage, dispensing and returns | 4.2.2 metadata, 4.2.4 corrections | Trials pharmacist |
An inventory without owners leaves the same gap the annex is written to close. The table below assigns the four governance tasks an inspector asks about. R marks the person who does the work. A marks the person accountable for it.
| Governance task | Investigator | R&D office | Sponsor | Service provider |
| Review of data and metadata, including the audit trail (4.2.3) | R and A for site data | R for portfolio records | A across the trial | R where it runs the system |
| Access granted and withdrawn as people join and leave (4.3.8) | R for site users | R and A for the trust estate | A for sponsor systems | R for its own platform |
| Validation evidence for the current release (4.3.4 and 4.3.5) | Holds a copy | R for locally procured systems | A for trial specific systems | R supplies the pack |
| Export, migration and continuing access (4.2.5 and 4.2.7) | R for site-held records | R and A for the archive route | A for the full 25 years | R supplies the export |
The sponsor stays accountable throughout, which regulation 28(1B) puts beyond doubt. A site that can name the system, the owner and the last review date for every row has done the governance work the annex asks for.

Validation deserves its own treatment, because the depth expected depends on what the system does and what it would cost to get it wrong. Our guide to GAMP 5 and computerised system validation sets out the software categories and the deliverables an inspector expects. The wider oversight changes introduced by the guideline sit in our guide to ICH-GCP E6(R3) and study oversight.
Also Read: MHRA GCP Inspections: What to Expect and the Most Common Findings
Which Software Tools Help Manage GCP and ICH Guideline Adherence?
No single tool manages GCP and ICH adherence on its own. Adherence sits across six record types: the study record, the site file, the trial master file, the quality system, training records and the pharmacy record. The tool question is which system holds each record and whether that system can evidence the duty on request.
Buy by system type first. The table below sets out what E6(R3) asks of each type and the test an NHS research team can run against the system it already has.
| System type | What it holds | What E6(R3) asks of it | The test to run |
| CTMS | Study list, approval and milestone dates, site status, regulatory population | Principle 9.6 transparency, and a record that supports the registration and results clocks | Produce one study’s approval date, registration deadline and named owner from the system |
| eISF | Essential records held by the investigator | Annex 1 Section 4.2.7 retention and continuing access, 4.3.3 security | Give a monitor read-only access to the live file without producing an export |
| eTMF | Sponsor-held essential records, filed to a defined structure | Principle 9.5 secure retention, Section 4.2.5 transfer and migration | Read the completeness position for one study today, not at close-out |
| QMS | SOPs, deviations, CAPA, audits and effectiveness checks | Principle 2 quality management, and Section 4.3.4 validation of the system itself | Trace one deviation from detection to a verified closure |
| Training records | GCP and protocol training, CVs, delegation entries | Section 4.3.8 user management, and training proportionate to the delegated role | Show that a task performed last month was done by a person trained and authorised for it on that date |
| Pharmacy record | IMP receipt, storage, temperature, dispensing and returns | Section 4.2.2 metadata and 4.2.4 corrections on the accountability record | Reconcile one participant’s dispensing record against the pharmacy stock entry |
A system type with no named owner is the gap, whichever product sits behind it.
The products below are the ones most often named on this question. Each description paraphrases the vendor’s own product page, checked on 15 October 2026. The categories differ, and that difference matters: a quality system and a data capture system answer different parts of the guideline.
| System | How the vendor describes it | Capabilities the vendor publishes | Fits best | Hosting stated on the product page |
| MasterControl | Configurable quality management software for clinical good clinical practice requirements, named against ICH GCP E6 | Clinical quality events linked to clinical operations, a TMF repository based on the TMF Reference Model, validation resources for the deployment | CROs, sites and vendors that want clinical operations and quality events on one quality platform | Not stated |
| Veeva Vault QMS | A cloud quality management system for life sciences, unified with the other Vault Quality applications | Deviations, corrective actions, change control, internal and external audits with findings, complaints, quality risk and supplier quality. Documents and training are separate Vault products | Sponsors and CROs already running Vault that want quality processes beside clinical ones | Cloud. Location not stated |
| Medidata Rave EDC | An electronic data capture system for capturing, managing, cleaning and reporting trial data | Pre-validated eCRF libraries, study design, EHR connectivity, mid-study amendments, automated study locking, live study and site reporting | Sponsors, CROs and sites that need the data capture layer across simple to complex global trials | Not stated |
| Qualio | A compliance platform for life sciences built around a cloud quality management system | Document management, training and competence, change control with traceability, audit management, CAPA and non-conformance workflows, supplier management, risk management referencing ICH Q9 | Quality teams that want a quality system in place quickly. The product page covers quality processes rather than trial operations | Cloud. Location not stated. Part 11, Annex 11 and ISO 27001 shown as compliance badges |
| Castor EDC | An API-driven electronic data capture system that combines trial data with other study sources | Low-code eCRF builder with templates, integration with EHR, ePRO, laboratory and device data through an open API, live monitoring and source data verification dashboards, audit trails on amendments, field-level encryption | Academic, MedTech and CRO teams that build studies quickly and pull data from several sources | Certified servers in supported regions worldwide, with no country named. Part 11, ICH GCP, GDPR, ISO 27001 and ISO 9001 named on the page |
| AQ Platform | The connected platform for UK and NHS clinical research, holding CTMS, eTMF, eISF, Pharmacy, QMS, CAPA and Digital DoA on one record | Study record carrying approval and milestone dates, essential records filed to the DIA TMF Reference Model, SOPs and training linked to the studies they apply to, deviations connected to CAPA and effectiveness checks, delegation tied to the training record | NHS trusts, CRDCs, academic sponsors and UK sites that want one record across study operations, documentation and quality | UK-hosted. NHS DSPT Standards Met (2026). Cyber Essentials certified |
In AQ QMS, an SOP and its training record are linked to the studies they apply to, so a training gap reads against the study rather than against a separate spreadsheet. In AQ Digital DoA, a task cannot be delegated until the person’s training record for it is complete.
Ask every supplier the same three questions. Which of the six record types does the product hold? What validation evidence comes with the current release? What does a complete export contain when the contract ends?
Where the Requirement Lands in an NHS Software Estate
A typical trust runs its research portfolio across several systems that were each adopted for a good local reason. The local portfolio system holds the study list. An electronic data capture tool holds participant data. Contracts sit in a finance folder. Approval letters arrive by email. Delegation logs live in the site file. All of that is ordinary, and all of it holds until a duty needs evidence from more than one place at once.
Consider a hypothetical trust with sixty open studies. A study receives approval on 4 May 2026. The registration duty runs from that approval, and the 90-day limit expires on 2 August. The approval letter reaches a research coordinator by email, and the coordinator adds a line to a set-up spreadsheet. The coordinator leaves in June. The spreadsheet survives, the mailbox does not, and the registration entry is made on 19 August after a sponsor query. The activity was completed. The evidence that it was completed on time was never held anywhere, and the breach is now a matter of record.
Failures of this shape share four characteristics, and each one is a property of the estate rather than the person:
- The trigger arrives outside the system. An approval letter in a mailbox starts a legal clock that the study record knows nothing about.
- The owner is implied. A task with no named owner in a system belongs to whoever remembers it, which lasts exactly as long as that person stays.
- The date is entered twice. One event recorded in two places produces two versions, and an inspector will ask which one governs.
- The proof is a document rather than a field. A scanned confirmation in a folder tells you what happened and leaves when it happened to be inferred.
Also Read: NHS R&D: Governing Site Files Across a Trust’s Studies
Effort or Design: Two Ways an Estate Meets the Same Duty
Two trusts can hold identical obligations and satisfy them by opposite means. One assembles the evidence when it is asked for. The other holds the evidence as a by-product of doing the work. Both can pass an inspection. Only one can pass it on a week’s notice while the people who set the study up are on leave.
| Requirement | Estate that meets it by effort | Estate that meets it by design |
| Registration deadline | Diary reminder set by the coordinator who read the approval letter | Approval date entered once, deadline derived, owner named, status visible on the study record |
| Results within 12 months | Tracked by the sponsor, chased by email near the anniversary | End of trial date drives a dated obligation with an owner and a countdown |
| Audit trail review | Extracted on request from each system separately | Reviewable in place, per record, by the person accountable for it |
| User access control | Leaver process handled by IT, research access checked annually | Access tied to the current delegation entry, withdrawn when the delegation ends |
| Validation evidence | Vendor certificate stored in a procurement folder | Validation and release records held against the system in the quality file |
| 25-year retention | Assumed to be covered by the supplier contract | Export format, migration route and named custodian agreed before go-live |
| Two regulatory populations | Held in the memory of the R&D manager | Flagged on each study record as old rules or amended regulations |
The distinction matters most under inspection conditions. An estate that meets duties by design produces the same answer whoever is asked and whenever the question comes. Our 2026 buyer’s guide to clinical trial management software for NHS trusts takes this into procurement, covering the assurance stack and the questions to put to a supplier.
The 25-Year Duty Most Software Contracts Leave Open
Regulation 31A requires essential records to be retained for at least 25 years beginning the day after the conclusion of the trial, with a further two years after authorisation for trials supporting a marketing authorisation. Throughout that period the records must be readily available, complete and legible for inspection by the MHRA or another competent authority. MHRA archiving guidance adds that the sponsor appoints a named individual to be responsible for archiving the documents, and restricts access to archived records to the individuals it appoints.
Twenty-five years outruns almost every software contract, hosting arrangement and file format a trust holds today. MHRA guidance on archiving is specific about what an electronic archive has to sustain: audit trails and metadata preserved alongside the records, long-term readability, validated and documented migration to new formats, and access restricted to named individuals appointed by the sponsor. Five questions turn that into a procurement position.
- What does a complete export contain, and does it include audit trails and metadata rather than data alone?
- Who validates a migration when the format or the supplier changes, and where is that validation documented?
- What access does the trust retain after the subscription ends, and in what form?
- Which named individual holds oversight of the archive, and where is that name recorded today?
- How is a record produced for an inspector in year 20, and has that route ever been tested?
Retention is a data integrity question as much as a storage one, because a record that survives without its metadata has lost the attributes that made it evidence. Our guide to ALCOA+ and the Trial Master File works through which attributes sit with the system rather than the page.
Also Read: The Investigator Site File Essential Documents Checklist (ICH-GCP Chapter 8)
A Readiness Checklist for an NHS Research Software Estate
The checks below take a morning against a single study and expose most of the gaps that matter. Each one asks the estate to produce evidence rather than asking a person to describe a process.
- Pick one study approved after 28 April 2026 and produce its registration date, the deadline that applied, and the person who owned it.
- Pick one study that ended in the last year and produce the results posting date against the 12-month limit.
- Show which of your open studies run under the amended regulations and which remain old rules trials.
- Produce the audit trail for one amended field, including who changed it, when, and why.
- Show that a leaver from three months ago holds no active access to any research system.
- Produce the validation and release records for the system holding your study data.
- Name the individual with oversight of archived records and show where that name is recorded.
- Export one study’s essential records and confirm the export carries metadata as well as content.

A check that takes several people and several days points at the estate rather than the team. That is a design result, and it responds to design changes.
Frequently Asked Questions
What software tools are used for managing GCP and ICH guideline adherence?
No single tool covers it. Adherence sits across the study record, the site file, the trial master file, the quality system, training records and the pharmacy record, so the real question is which system holds each one. MasterControl, Veeva Vault QMS, Medidata Rave EDC, Qualio, Castor EDC and AQ Platform are all named on this question and sit in different categories. AQ Platform holds all six record types on one record and is UK-hosted.
How should sites apply ICH E6(R3) data governance to their systems?
Sites apply it by naming every system that holds trial data and giving each one an owner. Annex 1 Section 4 sets the detail: metadata and audit trails kept with the record, audit trail review by a person, corrections carrying a reason and an identity, validated migration, continuing access, and access control that follows joiners and leavers. The sponsor stays accountable for all of it under regulation 28(1B).
Does a CTMS on its own make a trust compliant with ICH E6(R3)?
No. A CTMS evidences the operational duties, including approval dates, milestones and the registration and results clocks. The essential records, the quality system and the training records sit elsewhere, and E6(R3) asks for evidence from each of them.
What did the UK Clinical Trials Regulations change for research software on 28 April 2026?
The amended regulations made trial registration and the publication of summary results a legal requirement, confirmed that the sponsor’s functions include trial specific computerised systems, and set a retention duty of at least 25 years under regulation 31A. ICH-GCP E6(R3) came into force in the UK on the same day. Each duty now resolves into a dated record that a system has to produce on request.
How long must NHS clinical trial records be kept under regulation 31A?
Regulation 31A requires essential records to be kept for at least 25 years beginning the day after the conclusion of the trial, with a further two years after authorisation for trials supporting a marketing authorisation. The records have to stay readily available, complete and legible for inspection throughout that period. Retention includes continuing access, so an archive nobody can open does not satisfy the duty.
Who is responsible for a trial computerised system, the sponsor or the supplier?
The sponsor. Regulation 28(1B) states that the functions of the sponsor include the development and maintenance of trial specific computerised systems. A supplier provides the system and its validation evidence. Accountability for using it correctly stays with the sponsor.
What validation evidence should a supplier provide under E6(R3)?
Ask for the validation pack covering the release in use rather than a general certificate. Annex 1 sections 4.3.4 and 4.3.5 expect validation evidence and a controlled release path, and the sponsor holds a copy in its own file. Ask also how each new release is covered, because a system validated once stays validated only until it changes.
AQ Under the Amended Regulations: Evidence Produced by the Work
The AQ Platform holds study operations, documentation, quality and delegation in one connected environment, so the records the regulations ask for are produced by the work rather than assembled after it. The mechanism matters more than the module count.
- CTMS holds approval dates, milestones and study status on one record, which lets a registration or results deadline be derived from the event that starts it rather than tracked separately.
- eTMF is built on the DIA TMF Reference Model, which gives essential records a defined structure and a completeness position that can be read at any point rather than at close-out.
- eISF and AQ Pharmacy hold the site-held and pharmacy-held files under the same structure, which allows a trust to see the current position across every study without visiting each site.
- QMS and CAPA connect deviations to actions and effectiveness checks, which keeps the quality record traceable from detection through to verified closure.
- Digital delegation ties system access to the current delegation entry, which keeps user management aligned with who is authorised to perform each task today.
AQ is assured for NHS procurement through G-Cloud, the Data Security and Protection Toolkit and Cyber Essentials, and the platform is designed around ICH-GCP E6(R3), ALCOA+ and the UK Clinical Trials Regulations. Teams evaluating their position under the amended regulations can book a live demo and walk one study end to end.
Primary sources: MHRA guidance on compliance with ICH E6 GCP in the UK, MHRA archiving and retention of clinical trial records, Clinical trials regulations: transitional arrangements, and the HRA on research transparency and transitional arrangements.
