
Clinical trial management software for an NHS trust holds one operational record of every study the trust hosts. It has to satisfy three duties from that record: national delivery reporting through the CPMS milestone dates, MHRA inspection evidence, and NHS information governance assurance. The buying decision turns on portfolio scope rather than single-study scope.
A clinical trial management system (CTMS) for an NHS trust is the operational system of record for every study the trust hosts: who invited the site, when each set-up milestone was reached, which staff were delegated to which task, how recruitment is tracking, and what evidence exists behind each of those claims. The buying decision inside a trust differs from the sponsor decision in one respect that shapes everything else. A sponsor buys a CTMS to run studies it designed. A trust buys one to run a portfolio it did not design, under national delivery reporting, NHS information governance, and MHRA inspection at the same time.
That triple duty is the whole buying problem. A system that tracks one study well can still leave an R&D office assembling its national figures by hand every month, and still leave an inspector reading a reconstruction rather than a record. This guide sets out what NHS reporting actually asks of the system, what NHS procurement will require the supplier to evidence, what the amended UK Clinical Trials Regulations now expect of computerised systems, and how to tell the two shapes of product apart before a shortlist is drawn.
Key Takeaways for NHS R&D Buyers
- The three obligations an NHS trust CTMS has to satisfy from one record
- The national delivery metrics and the six CPMS milestone fields a site must maintain
- Where a trust’s study record breaks, with the named artefacts involved
- The assurance pack NHS procurement expects: DSPT, Cyber Essentials, DTAC, DPIA and clinical safety
- What ICH-GCP E6(R3) requires of trial specific computerised systems from 28 April 2026
- A supplier question set an R&D office can use before shortlisting
Why Does an NHS Trust Buy a CTMS Differently From a Sponsor?
Three separate audiences read the same trust study record, and each one reads it for a different purpose. National delivery reporting reads it for milestone dates. An MHRA inspector reads it for evidence that the trial ran the way the records claim. NHS information governance reads it for the security and lawful basis under which the data is held at all. A sponsor CTMS answers the first two for its own studies. A trust needs all three answered across a portfolio of studies belonging to many sponsors.
The national picture explains why this now carries weight. The Department of Health and Social Care publishes monthly UK Clinical Research Delivery key performance indicators, and the split in that data is consistent. Regulatory approval runs close to its target. Local set-up lags it by a wide margin. In the release covering data to July 2026, 98% of studies received a combined review decision within 60 days against a 99% target, while 56% of studies opened to recruitment within 60 days of approval against a 90% target. Our breakdown of the UK clinical research delivery KPIs walks all seven indicators in detail.
The gap sits inside the trust. It is made of contract signatures, pharmacy sign-off, capacity confirmation, staff delegation and data entry, and every one of those is a record the trust already holds somewhere. A CTMS earns its place in an R&D office by holding them once.
The approval clock is nearly solved. The local clock is the one a trust can still move.

What Does National Reporting Require From the System?
Study data reaches the national picture through the Central Portfolio Management System (CPMS), which the NIHR Research Delivery Network owns and manages. Most trusts feed it from a Local Portfolio Management System (LPMS) rather than keying directly. UKCRD has deliberately kept the site-level core to six essential fields, and the guidance is explicit that all six must be completed, in chronological order, for a study to count in the data at all.
| Field | What the date marks | Why it is easy to get wrong |
| Date site invited | The sponsor email providing the near final or final protocol | Arrives in an individual inbox before any study record exists |
| Date site selected | The sponsor asks the site to begin set-up after due diligence | Confused with the expression of interest that preceded it |
| Non-confirmation status | Sponsor declined, site declined, or null response | Left blank when a study quietly stalls rather than formally stops |
| Date site confirmed | The last contract signature across all organisations involved | Recorded when the trust signed, rather than when the last party did |
| Date site ready to start | The sponsor gives green light for the site to recruit | Sits with the sponsor, so the site learns it by email |
| First patient first visit | The first study visit of the first participant | Known in clinic days before it reaches the LPMS |
Two of those fields changed weight in January 2026. The 60-day site set-up metric now ends at the Date Site Confirmed rather than at Date Site Ready to Start, on the basis that the wait for sponsor green light sits outside site control. The 30-day recruitment metric still starts at Date Site Ready to Start. The consequence is arithmetical and catches R&D offices out: the two site metrics no longer sum to elapsed time. Alongside these sits a separate policy expectation that participating sites complete set-up within 90 days, formed of the 60-day and 30-day parts, inside the government’s 150-day study-level target.
Published trust-level performance shows how wide the spread is. In the UKCRD trust-level set-up report cut on 3 August 2026, University Hospital Southampton NHS Foundation Trust recorded 100% of eight studies set up within 90 days, and Liverpool University Hospitals NHS Foundation Trust recorded 100% across five. The Newcastle upon Tyne Hospitals NHS Foundation Trust combined the highest volume in the cohort with strong performance, at 81% across 21 studies and a median of 46 days. Across the rest of the distribution, most trusts sit well below the target, and the operational difference is rarely clinical capacity. It is how quickly the trust can see where a study has stopped.
Also Read: CPMS and LPMS: What Sites Must Enter and When
Where Does the Study Record Break Inside a Trust?
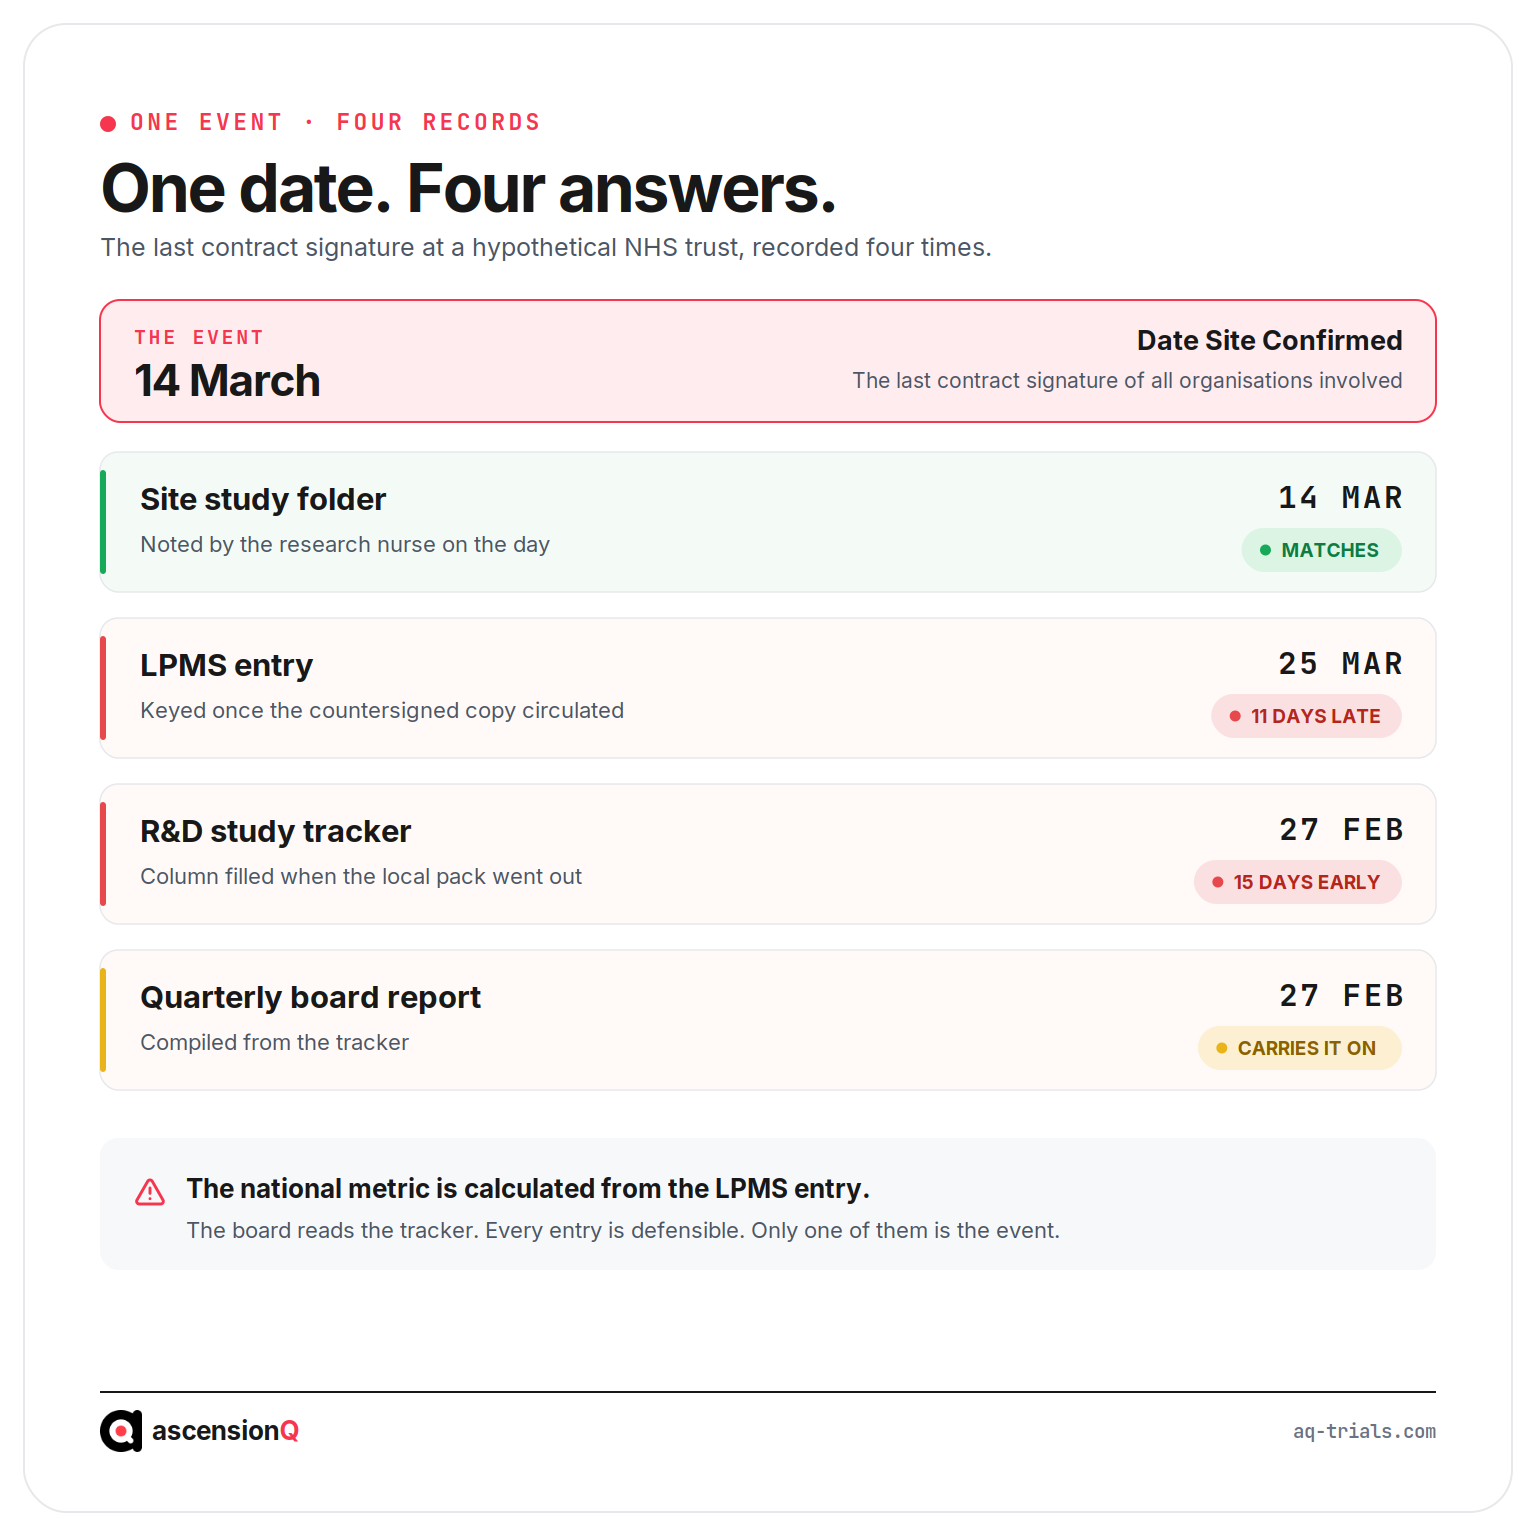
The failure is a copying failure, and it happens in the ordinary course of a competent week. Take a hypothetical multi-site commercial study at an NHS trust. The last contract signature lands on 14 March. That single event then enters four records at four different moments, and each entry is defensible on its own terms.
- The research nurse notes 14 March in the study folder on the day it happens.
- The LPMS entry is keyed on 25 March, once the countersigned copy circulates.
- The R&D study tracker already carries 27 February, filled in when the local information pack went out.
- The quarterly board report is compiled from the tracker, so it carries 27 February onward.
The national metric is calculated from the LPMS entry, which reports the study eleven days slower than it was. The board reads the spreadsheet, which reports it fifteen days faster than it was. Nobody made an error. The record was simply kept in four places, and four places is four answers.
The same pattern reaches the artefacts an inspector asks for. A delegation of authority log signed in April, covering a task performed in March, produces a documented gap in authorisation. A visit recorded outside its protocol window becomes a deviation with no linked CAPA. A site file version that never matched the sponsor’s copy becomes a reconciliation exercise during the inspection itself. Our guide to MHRA GCP inspections and the most common findings covers what inspectors write up most often, and the control that prevents each one.
Every entry was defensible. Only one of them was the event.
What Must a Supplier Evidence Before NHS Procurement Clears It?
NHS assurance is a stack rather than a checklist, and the layers belong to different parties. A supplier holds some of it. The trust holds the rest, and cannot delegate its own layer to a vendor. R&D offices lose weeks by discovering that split late.
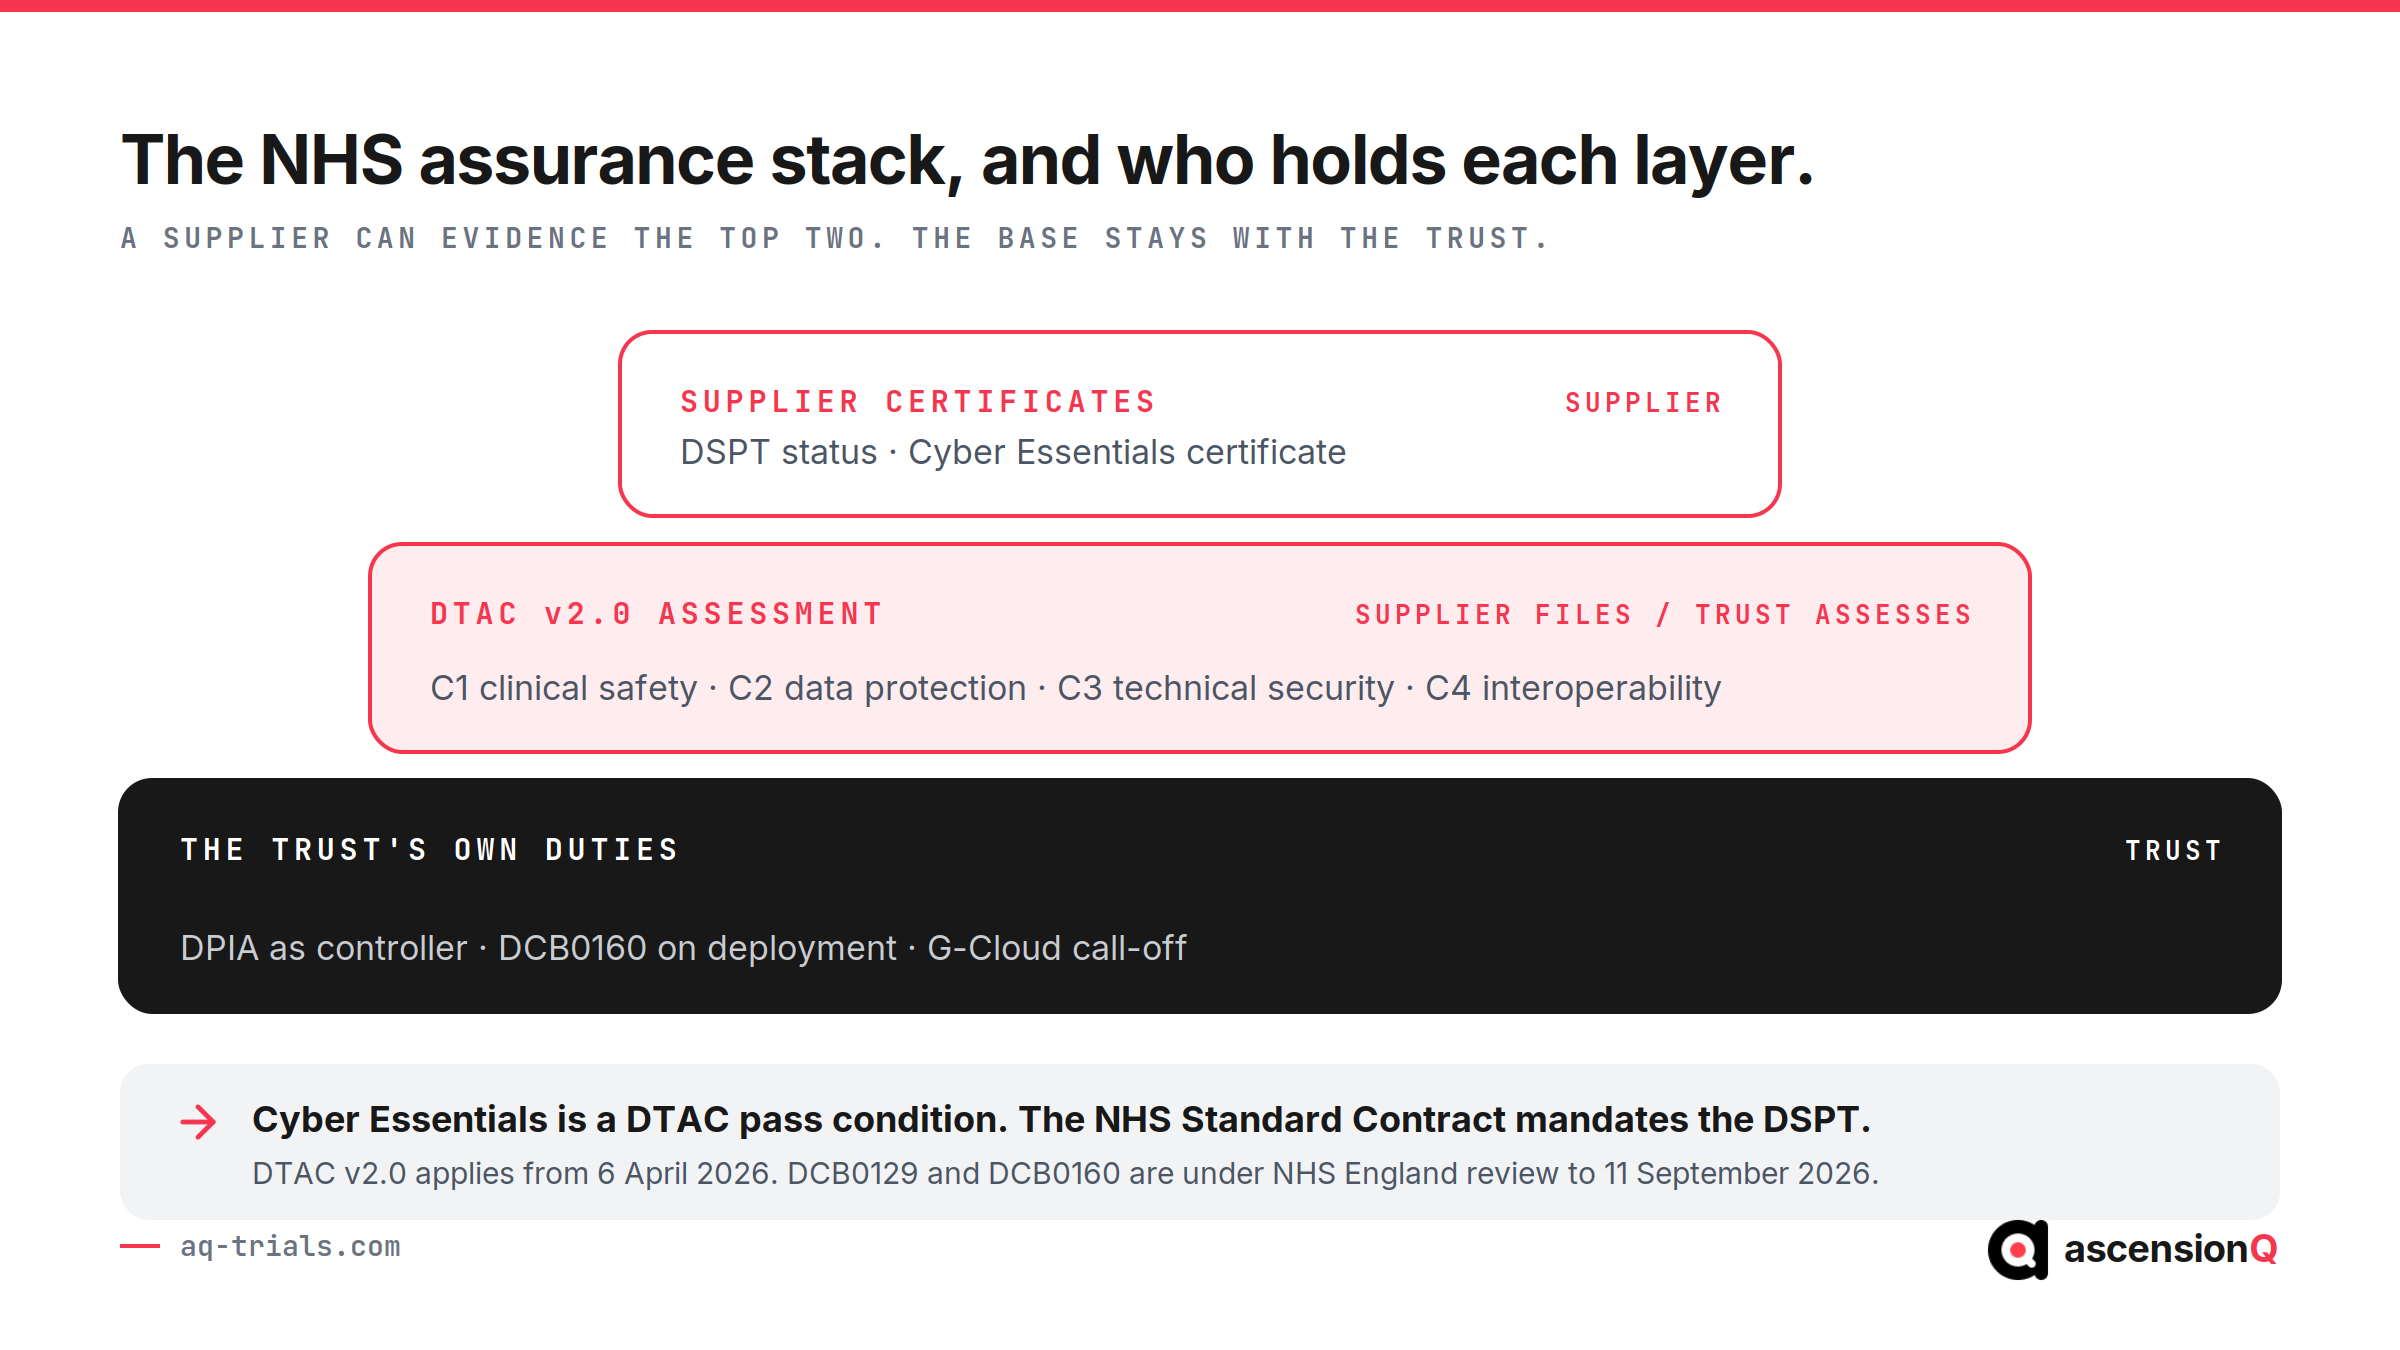
| Assurance item | What it establishes | Who holds it | Published pass condition |
| Data Security and Protection Toolkit | Annual information governance self-assessment against the National Data Guardian standards | Supplier and trust submit separately | Standards Met or Standards Exceeded, published by 30 June each year |
| Cyber Essentials | Five technical controls: firewalls, secure configuration, update management, user access control, malware protection | Supplier | Valid certificate, 12-month validity, verifiable on the IASME database |
| DTAC v2.0 | Clinical safety, data protection, technical security, interoperability, usability | Supplier completes, trust assesses | Sections C1 to C4 must pass; D1 is scored to compare products |
| Data Protection Impact Assessment | Lawful basis and risk mitigation for processing participant data | Trust, as controller, informed by the supplier’s own DPIA | Completed in advance of processing under UK GDPR |
| DCB0129 and DCB0160 | Clinical risk management for health IT, manufacturer side and deploying organisation side | Supplier and trust respectively | Applicability decided by NHS England’s six-step test |
| G-Cloud call-off | Compliant route to contract for cloud software | Trust | Direct award only; 36 months plus an optional 12-month extension |
Four points inside that stack repay attention during a procurement.
- DSPT status wording matters. “Approaching Standards” means the organisation published a Standards Not Met assessment and had a remediation plan approved. Ask which status a supplier holds and for which assessment year, since the toolkit runs on a 30 June annual cycle. NHS trusts themselves moved to the CAF-aligned toolkit for 2024-25; IT suppliers remain on their own evidence set.
- Cyber Essentials sits inside DTAC. Question C3.1 of DTAC v2.0 requires a valid Cyber Essentials certificate to pass technical security. The NHS Standard Contract mandates the DSPT, so treat Cyber Essentials as an assessment requirement rather than a contractual one.
- The DPIA stays with the trust. DTAC states that the manufacturer’s DPIA should be used by the NHS organisation when completing its own, as controller. A supplier DPIA is an input, and the trust’s obligation survives it.
- Clinical safety applicability is settled by a published test. NHS England’s decision guidance turns on whether the product is used to influence, support or manage real-time or near-real-time direct care. A supplier who considers DCB0129 inapplicable must supply a written rationale, and DCB0160 clause 2.5.1 still puts the confirming duty on the deploying organisation. Both standards are currently under NHS England review, with a public consultation open until 11 September 2026.
One procurement mechanic catches teams out repeatedly. G-Cloud is a direct award framework. Running a mini-competition, RFP, RFQ or ITT through it breaches the terms of the agreement, and prices and terms are fixed at the point of tender. A trust that wants a competitive evaluation should shortlist on published service definitions and award directly, or use a framework designed for competition.
Also Read: NHS R&D: Governing Site Files Across a Trust’s Studies
What Does ICH-GCP E6(R3) Now Require of the System Itself?
The amended UK Clinical Trials Regulations, made as SI 2025 No. 538, came into force on 28 April 2026. From that date, compliance with the ICH E6 good clinical practice principles is a legal requirement in the UK under Regulation 28, and the MHRA has been specific that the principles rather than the entire guideline carry legal force, with the annexes standing as relevant guidance that cannot be ignored.
One clause changes the software conversation directly. Regulation 28(1B) confirms that the functions of the sponsor include functions in relation to the development and maintenance of trial specific computerised systems, and the selection and oversight of a laboratory. System selection is now named regulatory territory rather than an IT preference. On the site’s side of that oversight, lab sample management software records each sample from collection to reconciliation.
- The system holds a validated audit trail, which lets a trust show when a milestone date was recorded and by whom rather than asserting it.
- Delegation is checked at the point a task is assigned, which prevents a signature dated after the activity it authorises.
- Risk signals surface against the live record, which supports the risk-proportionate oversight E6(R3) expects instead of a periodic manual review.
- Validation evidence is available on request, which shortens the trust’s own assurance work at DTAC and DPIA stage.
Trials that started before 28 April 2026 need a documented impact assessment of the GCP updates rather than an automatic transition, and a trust’s system should be able to evidence which of its studies fall on each side of that line. Our guides to the new UK Clinical Trials Regulations and to ICH-GCP E6(R3) and CTMS oversight cover the wider change. The MHRA’s own position is published in its guidance on compliance with ICH E6 in the United Kingdom.
Which Kind of System Is the Trust Actually Buying?
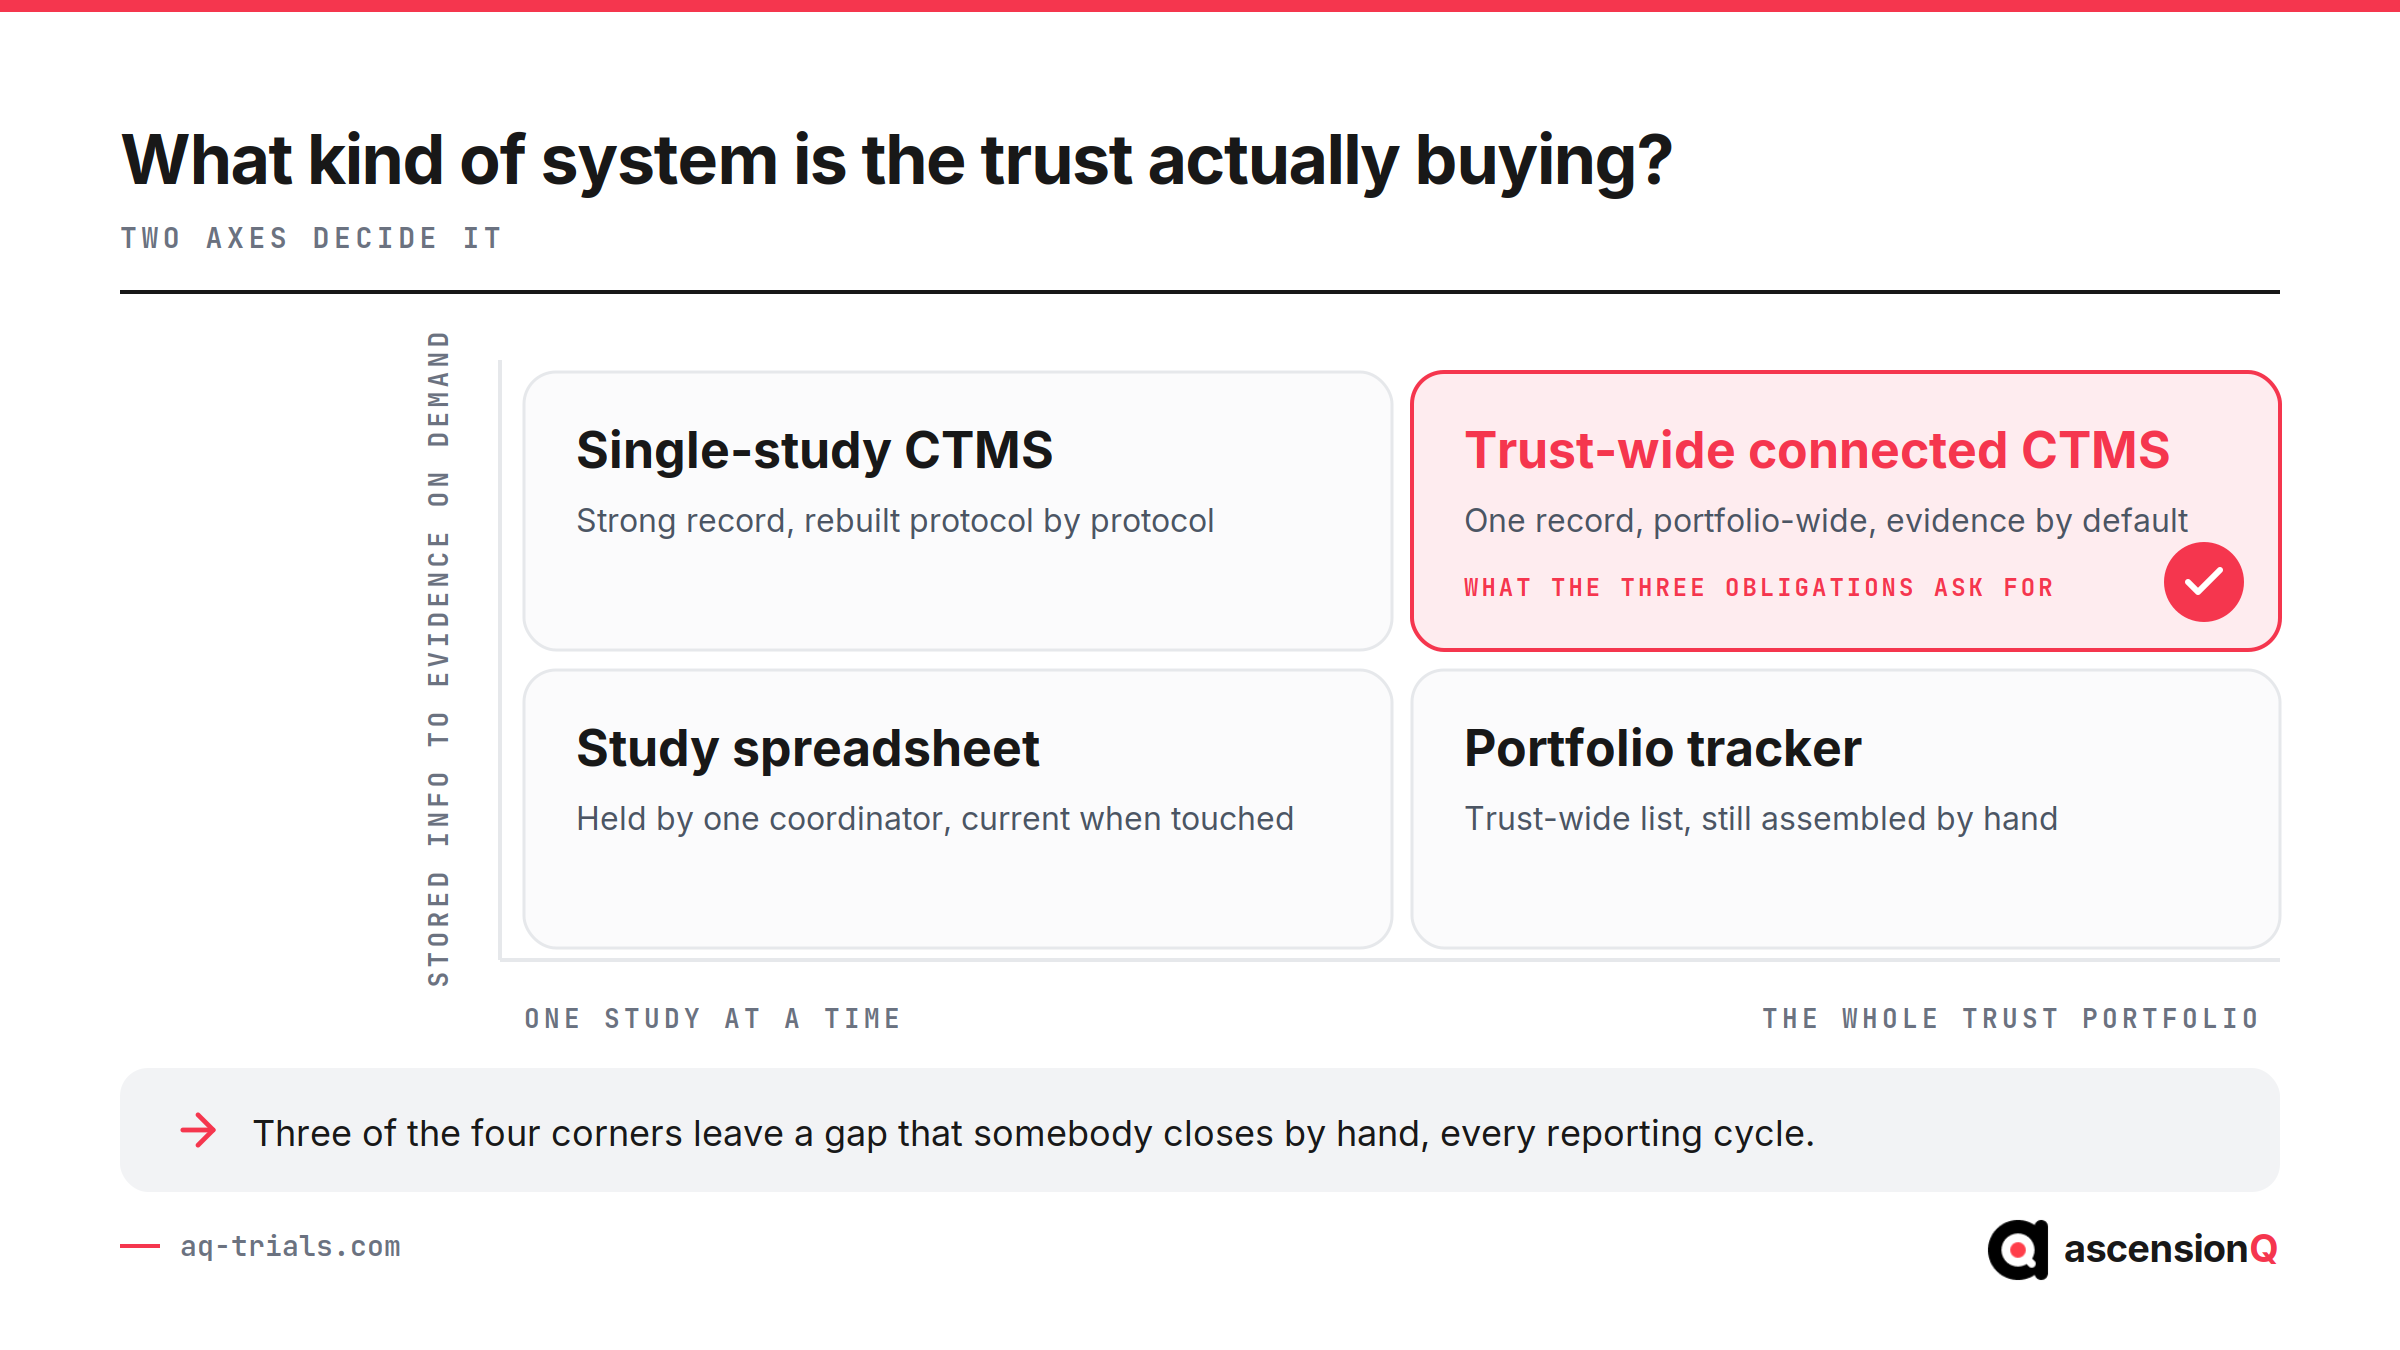
Two axes separate the products on a shortlist. The first is scope: one study at a time, or the whole trust portfolio. The second is what the system leaves behind: stored information that somebody assembles into evidence later, or evidence available on demand. Most disappointing purchases are a mismatch on the second axis, because both kinds of product demonstrate well.
| Dimension | Study-by-study record | Portfolio-wide governed record |
| Where a milestone date lives | In the study’s own tracker, keyed again into the LPMS | Recorded once, read by the LPMS export and the board report |
| Answering “which studies are past 60 days?” | A manual sweep by whoever maintains the tracker | A live view, available to any authorised user |
| Delegation currency | Reviewed at the next monitoring visit | Enforced when the task is assigned |
| What an inspector sees | A reconstruction assembled from several sources | The record the team actually worked in |
| Effect of a staff change | Local knowledge leaves with the person | The record stays, permissions move |
| Information governance position | Assessed per system and per study | Assessed once, at platform level |
| Pharmacy and site file linkage | Held in separate files, reconciled on request | Linked to the same study record |
A trust that hosts a handful of studies can run the left-hand column well. A trust reporting monthly against national metrics across dozens of studies cannot, because the reconciliation cost scales with the portfolio while the R&D team does not. Our comparison of CTMS versus spreadsheets for capacity planning shows the same effect on the staffing side.
What Is the Best Clinical Trial Software for NHS Clinical Research Facilities?
The best clinical trial software for an NHS clinical research facility is the system that carries the facility’s whole portfolio and produces inspection evidence from it on demand. Facilities comparing options name EDGE Research Management, REDCap, CRFManager, Veeva CTMS, Medidata Clinical Cloud and AQ. Each publishes a different scope, and the scope decides the shortlist.
Each entry below states what the vendor publishes on its own product page, read on 5 November 2026. Prices are left out, because most of these vendors publish none. Our guide to clinical trial management system cost covers the pricing models the market does publish.
| System | What the vendor states it is | Published availability | What the vendor’s page states about NHS or UK use |
| EDGE Research Management | A research management system whose published key features include version-controlled document management, electronic delegation logs, participant management and recruitment, a workflow builder and a finance module for invoice tracking | Subscription for subscribers, delivered from a secure Microsoft Azure environment | The features page states no NHS or UK scope; the site credits EDGE Clinical Research to the University of Southampton |
| REDCap | A secure web application for building and managing online surveys and databases, geared to online and offline data capture for research studies and operations | Free to non-profit organisations that join the REDCap Consortium, whose partners run and support their own individual systems | The site names data capture only and states no NHS or UK position |
| CRFManager | A web-based resource management system with two components, study management and resource management, developed by the University of Edinburgh Clinical Research Facility | Non-exclusive licence to not-for-profit organisations only, with hosting at the University of Edinburgh and training included | Built inside a UK clinical research facility; the licence page states no NHS assurance position |
| Veeva CTMS | An enterprise trial management system providing end-to-end study management and monitoring capabilities | Part of the Veeva Clinical Operations suite, whose applications share a common data model in one Vault | The page positions the suite for sponsors and contract research organisations and states no NHS position |
| Medidata Clinical Cloud | A CTMS that brings clinical and operational activity into one connected, AI-enabled solution, covering visit monitoring, issue management, oversight and reporting, document tracking, ICF review and study management | Part of the Medidata platform, published as supporting both sponsor-led and CRO-managed trials | The page states no NHS or UK position |
| AQ Platform | AQ CTMS holds a trust’s whole study portfolio as one operational record, with AQ eISF, AQ Pharmacy, AQ Digital DoA, AQ QMS and AQ CAPA working against that same record | UK-hosted platform, validated to GxP standards with every release | NHS DSPT Standards Met (2026), Cyber Essentials certified, six years of continuous daily NHS use |
A clinical research facility and an R&D office read that table from different ends. A facility weighs daily workflow, resource scheduling and the recruitment record. An R&D office weighs the inspection position, which our guide to choosing a CTMS for NHS R&D sets out against nine named attributes. For the wider comparison across the market, see how to choose clinical research software.
What Should an R&D Office Ask Before Shortlisting?
The questions below separate the two shapes of product quickly, because each one has a demonstrable answer rather than a positioning answer. Ask for the answer to be shown in the product during the demonstration.
- Show me every study in the portfolio past its 60-day set-up point, right now. A portfolio-level view answers in one screen. A study-level product answers by export.
- Where do the six CPMS milestone fields live, and how do they reach our LPMS? Establish whether the dates are entered once or twice.
- Show me the audit trail for a milestone date that was later corrected. This tests the record rather than the interface.
- What happens when an unauthorised staff member is assigned a delegated task? A control that blocks at assignment differs from a report that flags it afterwards.
- Which DSPT status do you hold, for which assessment year? Ask for the published entry rather than a statement.
- Provide your Cyber Essentials certificate and your completed DTAC v2.0 form. Both are documents, so they can be requested before a shortlist rather than after.
- Provide your product DPIA and your validation documentation. These feed the trust’s own DPIA and its DCB0160 work.
- How does the site file and the pharmacy file connect to the study record? Separate systems mean separate reconciliations at every monitoring visit.
What Are the Risks of Buying the Wrong Shape of System?
- National figures are compiled by hand each month, so the reported position lags the operational one and improvement work targets stale data.
- Milestone dates differ between the LPMS, the study tracker and the board report, which makes performance discussions a debate about the numbers.
- Delegation gaps surface during monitoring rather than at assignment, which converts an avoidable control into an inspection finding.
- Each additional system carries its own DPIA, its own DSPT dependency and its own access review, which multiplies governance overhead across the portfolio.
- Inspection preparation becomes a project, because the evidence exists in fragments that have to be assembled under time pressure.
- Study knowledge concentrates in individuals, so staff turnover removes the ability to answer questions about historic studies.
Also Read: Why NHS Sites Miss the 90-Day Set-Up Target and How to Close It
How Do I Replace Our Current Trial Management System?
A system replacement runs in five stages: export the record the old system holds, validate the new system against your own studies, run both in parallel for an agreed period, cut over study by study, then archive the old system in a readable form. The export is the stage that decides whether the rest is possible.
| Stage | What the trust does | What it holds at the end |
| 1. Export | Agree the export format with the incumbent supplier in writing, then take every study record with the audit trail behind it | A complete, readable copy of the old record that stands up without the old software |
| 2. Validate | Test the new system against the trust’s own studies, roles and reporting outputs, and record the evidence as you go | Validation evidence the trust can produce at DTAC and DPIA stage |
| 3. Parallel run | Enter one full reporting cycle in both systems and reconcile the milestone dates line by line | Proof that the new system reproduces the position the trust reports nationally |
| 4. Cut over | Move studies one at a time, starting with those at a natural break such as set-up or close-out | A dated record of which study moved when, and which system held each date |
| 5. Archive | Keep the old record complete, legible and retrievable for the statutory retention period | An archive the licensing authority can read without access to the retired system |
Which Records Must Leave the Old System?
- The six CPMS milestone dates for every study, each with the audit trail that shows when it was recorded and by whom.
- Delegation records with their effective dates, so the authorisation history survives the move.
- Document versions, rather than the current version of each document alone.
- Recruitment figures, visit records and screening data for every study in the portfolio.
- Deviation and CAPA records, with the link between each deviation and the action that closed it.
- User accounts, roles and access history, which an inspector reads alongside the delegation log.
Regulation 31A of the Medicines for Human Use (Clinical Trials) Regulations 2004, as amended, requires the documents it covers to be kept for 25 years beginning with the day after the conclusion of the trial, to remain complete and legible, and to be readily available to the licensing authority on request. It covers documents held in electronic form, and it requires any alteration to a document to be traceable. A migration that carries current values and leaves the audit trail inside a system the trust is switching off satisfies the first duty and breaks the other two.
How Long Should Both Systems Run in Parallel?
The reporting cycle sets the parallel period, rather than a fixed number of weeks. One full monthly cycle entered in both systems and reconciled gives the R&D office a direct check that the new system reproduces the figures it reports nationally, and it surfaces any field the export mapped to the wrong place. Our guide to implementing and using a CTMS covers the rollout sequence around that period, and the regulations section above explains why system selection now sits inside sponsor oversight rather than inside IT preference.
Also Read: DSPT and Cyber Essentials: What NHS Procurement Expects of Research Software
Frequently Asked Questions
What Is the Best Clinical Trial Software for NHS Clinical Research Facilities?
The best system for a clinical research facility depends on the portfolio it carries. Facilities comparing options look at EDGE Research Management, CRFManager, Veeva CTMS, Medidata Clinical Cloud and AQ, with REDCap used for data capture alongside one of them. The deciding test is whether the system produces inspection evidence on demand or stores information somebody assembles later.
I Need to Replace Our Current Trial Management System: Where Do I Start?
Begin with the record the current system holds. List every study in it, the milestone dates and audit trail behind each one, and the retention duty attached to each. Agree the export format with the incumbent supplier in writing. Then plan a parallel period, validate the new system against your own studies, and set a cut-over date study by study.
What Should an NHS Trust Export From Its Old CTMS?
Export the six CPMS milestone dates per study, the audit trail behind every date, delegation records with their effective dates, document versions, recruitment figures and any deviation and CAPA records. Regulation 31A requires the documents it covers to be kept complete, legible and readily available to the licensing authority for 25 years after a trial concludes, so exporting current values alone leaves a gap.
Who Should Sit on an NHS Trust CTMS Evaluation Team?
Six roles carry a decision each. The R&D office owns the portfolio and the reporting requirement. Information governance owns the DPIA. The clinical safety officer owns the DCB0160 position. Pharmacy owns the accountability records. Procurement owns the route to contract. A research nurse or coordinator owns the daily workflow the system has to fit.
How Does AQ Support NHS Trust Research Delivery?
AQ CTMS holds the trust’s study portfolio as one operational record, so a milestone date is entered once and read everywhere it is needed. Set-up milestones, recruitment, visit scheduling and site status sit in the same place, which gives an R&D office a live portfolio position instead of a monthly reconstruction. Our work with NHS and hospital research teams is built around that reporting duty.
The surrounding modules close the artefacts an inspector asks for, against the same study record.
- AQ eISF holds essential site documents in a controlled electronic investigator site file, which lets a monitor review between visits rather than only during them.
- AQ Pharmacy keeps pharmacy accountability in its own separately owned file, which preserves the separation MHRA inspection expects while linking it to the study.
- AQ Digital DoA records delegation with effective dates mapped to training and qualification evidence, which stops authorisation gaps forming.
- AQ QMS and AQ CAPA carry controlled documents, training and corrective action, which links a deviation to the action that closed it.
- AQ eTMF is built on the CDISC TMF Reference Model, which gives sponsor and site a shared structure to reconcile against.
On the procurement side, AQ holds NHS DSPT Standards Met (2026), is Cyber Essentials certified, runs on a UK-hosted platform with ISO 27001-aligned controls, and provides validation, data protection and governance evidence to trust teams as an assurance pack. University Hospitals of Liverpool Group launched AQ eISF across a 150+ study portfolio, and Royal Free London brought controlled documents, training and CAPA into one quality system used by 300+ people.
See how the portfolio view, the site file and the delegation record behave against your own studies. Book a live demo and bring the questions from the shortlisting list above.
