
ICH E6(R3) requires the investigator or institution at a trial site to hold responsibility for investigational medicinal product (IMP) management, to keep records of delivery, inventory, use by each participant, return and destruction, and to store and use every unit as the sponsor and the approved protocol specify. Section 2.10 of Annex 1 sets those duties out in nine clauses. A UK site reads them against the ICH E6 GCP Principles, which became a legal requirement here on 28 April 2026.
This guide takes section 2.10 clause by clause, sets out the conditions attached to delegating IMP management to a pharmacist, and shows where the site’s duty ends and the sponsor’s begins. It sits under the guide to IMP accountability in clinical trials, which covers the wider record and how it reconciles.
- The ICH E6 GCP Principles carry legal force in the UK from 28 April 2026, and Annex 1 section 2.10 is relevant guidance a site has regard to.
- Clause 2.10.1 places responsibility for IMP management with the investigator or institution, and allows the sponsor to facilitate parts of it.
- Clause 2.10.2 permits delegation to a pharmacist or another individual, who then works under the investigator’s oversight.
- Clause 2.10.4 fixes the content of the record, down to batch numbers, expiry dates and the unique codes assigned to product and participant.
What Is the Legal Status of ICH E6(R3) at a UK Site?
ICH E6(R3) holds two statuses at a UK site at once. Paragraph 1 of Part 2 of Schedule 1 to the Medicines for Human Use (Clinical Trials) Regulations 2004 now requires trials to be “conducted in accordance with the principles of good clinical practice set out in the International Council for Harmonisation of Technical Requirements for Pharmaceuticals for Human Use Guideline for Good Clinical Practice, as amended from time to time”. The 2025 amending regulations substituted that wording with effect from 28 April 2026.
The MHRA draws the boundary in its guidance on compliance with ICH E6 in the United Kingdom: compliance with the GCP Principles, rather than the entirety of the guideline, is the legal requirement from that date. A separate retained UK principle requires the investigator and sponsor to have regard to all relevant guidance, and the MHRA draws the conclusion itself: the annexes to ICH E6(R3) cannot be ignored, because they are relevant guidance.
Section 2.10 is guidance. The duty it describes is still tested at inspection.
| Source | Status at a UK site | What it settles for pharmacy |
|---|---|---|
| ICH E6 GCP Principles | Legal requirement from 28 April 2026 | The quality and proportionality expectations every pharmacy record answers to |
| ICH E6(R3) Annex 1 section 2.10 | Relevant guidance the site must have regard to | The clause-level expectations an inspector works from |
| Regulation 29 of the 2004 Regulations | Legal requirement | No trial may run other than in accordance with its protocol, which gives clause 2.10.6 legal force |
The UK-specific annotations to ICH E6(R3) map individual clauses onto the domestic regulations. The annotation against clause 2.10.5 sends storage arrangements back to the trial protocol, and the one against essential records sends retention to regulation 31A.
What Does Section 2.10 Require, Clause by Clause?
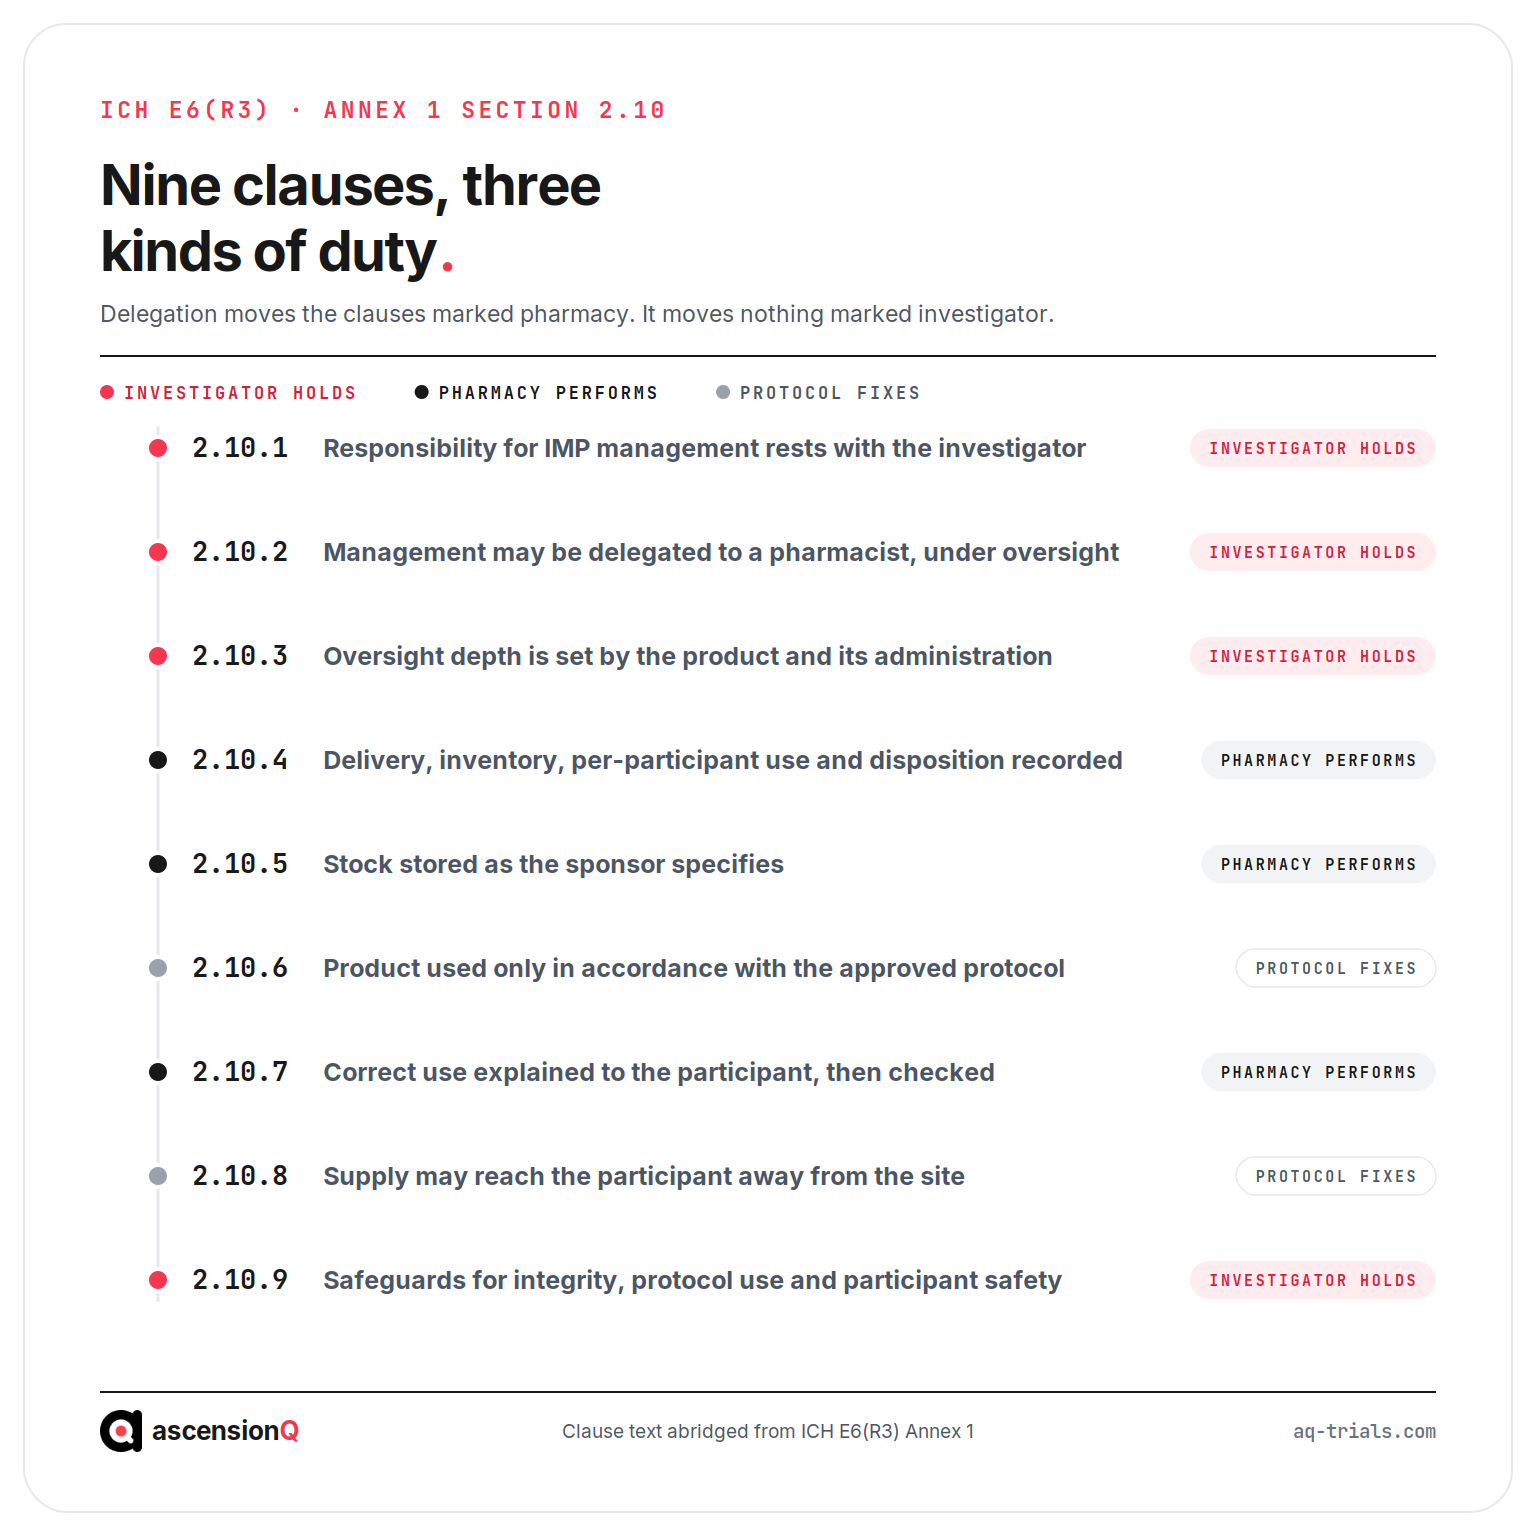
Section 2.10 requires nine things of the site, each landing on a different part of the pharmacy’s week. The table pairs each clause with the action it asks for.
| Clause | What ICH E6(R3) says | What the site does about it |
|---|---|---|
| 2.10.1 | Responsibility for IMP management, including accountability, handling, dispensing, administration and return, rests with the investigator or institution | Names the accountable party, and treats sponsor forms and systems as facilitation rather than transfer |
| 2.10.2 | Delegation of some or all IMP management to a pharmacist or another individual, per local regulatory requirements, under the investigator’s oversight | Records the delegation and who provides the oversight |
| 2.10.3 | Oversight depth depends on the product’s characteristics, the route and complexity of administration, existing safety knowledge and marketing status | Sets review frequency and depth study by study, and writes the reasoning down |
| 2.10.4 | Records of delivery, inventory, use by each participant, return and disposition, carrying dates, quantities, batch numbers, expiry dates and the unique codes for product and participant | Maintains the log at unit level, every field populated at the time of the action |
| 2.10.5 | Storage as the sponsor specifies and in accordance with applicable regulatory requirements | Holds stock under the protocol’s conditions and evidences them continuously |
| 2.10.6 | Use of the product only in accordance with the approved protocol | Dispenses against a prescription matching the protocol’s dose and schedule |
| 2.10.7 | Explanation of correct use to each participant, with checks at appropriate intervals that instructions are followed | Counsels the participant at dispensing, and records the later checks |
| 2.10.8 | Shipment to the participant’s location, or supply closer to them, with administration by site staff, the participant, a caregiver or a healthcare professional | Extends the unit-level record to handovers outside the hospital |
| 2.10.9 | Management per applicable regulatory requirements, with safeguards for product integrity, protocol-compliant use and participant safety | Runs the process under a controlled procedure rather than local habit |
Two clauses carry more record weight than the rest. Clause 2.10.5 generates the storage record set, covered in the investigational product storage records checklist. Clause 2.10.8 adds handovers beyond the pharmacy door, each one walked through in the twelve steps a trial medicine takes from depot to patient.
Also Read: What Is an Investigational Medicinal Product?
Who May the Investigator Delegate IMP Management To?
The investigator may delegate some or all IMP management to a pharmacist or another individual. Clause 2.10.2 attaches three conditions, and all three hold at once.
- The delegate is a pharmacist or another appropriate individual. The clause names the pharmacist first, which is why a UK trial pharmacy service usually holds this work.
- The delegation follows local regulatory requirements. The arrangement satisfies the rules governing the supply of medicines at that organisation, which keeps the trial record inside its own medicines governance.
- The delegate works under the investigator’s oversight. Oversight is an activity with its own evidence, so the record shows the review happened rather than asserting it exists.
Delegation moves the task. Clause 2.10.1 leaves the responsibility where it was.
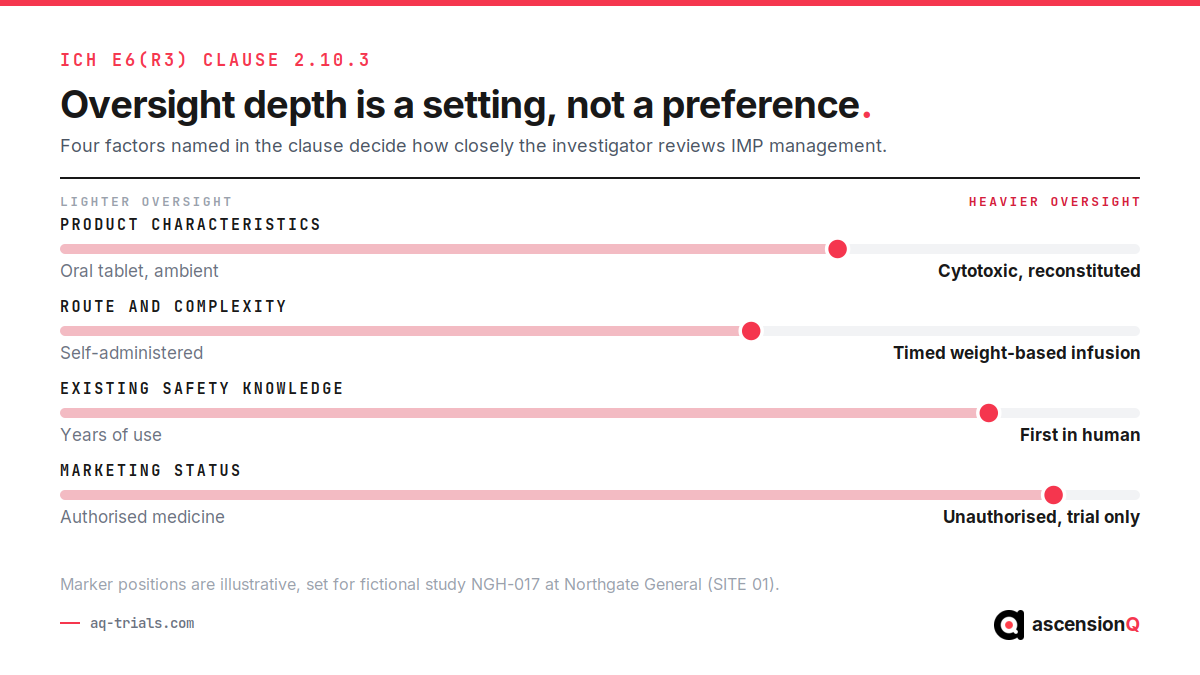
Clause 2.10.3 then decides how deep that oversight goes. It names four factors: the characteristics of the product, the route and complexity of administration, existing knowledge of its safety, and its marketing status. A site that applies them consistently spends its review effort where the product warrants it, and writes down the reasoning that set the level.
The tiers behind that delegation, role by role, are set out in who is accountable for IMP at a trial site. Authority to act belongs in the study delegation record, and an entry signed by someone absent from it fails clause 2.10.2 even where the count is correct.
What Must the Record Under Clause 2.10.4 Contain?
Clause 2.10.4 fixes the scope of the record and the fields inside it. The scope covers four events in a unit’s life: delivery, inventory, use by each participant including evidence they received the protocol dose, and return or destruction. Five data elements run through every entry: dates, quantities, batch or serial numbers, expiry dates, and the unique codes assigned to product and participant. The batch number is what lets a recall reach the right people, and the pair of codes ties one kit to one person without naming them, which lets a blinded record stay blinded.
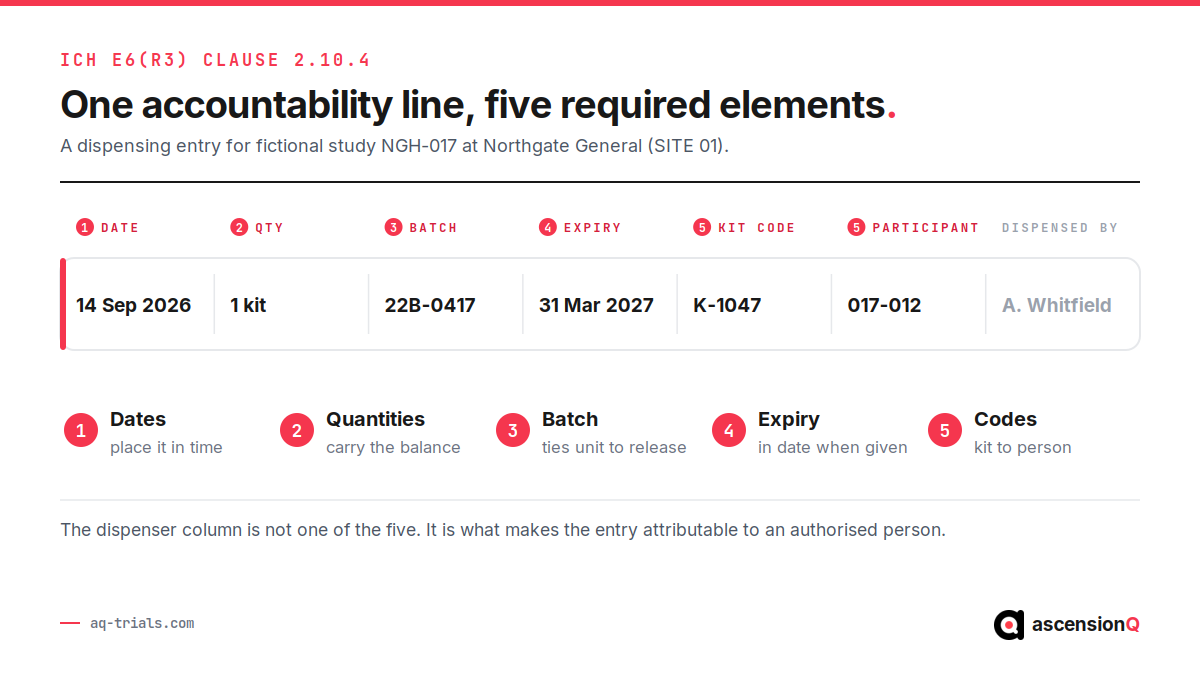
A worked example shows the standard. At fictional study NGH-017 at Northgate General (SITE 01), kit 1047 is dispensed to participant 017-012 on 14 September 2026. A compliant line carries that date, one kit, batch 22B-0417, expiry 31 March 2027, the kit and participant codes, and the authorised person who dispensed it. A line reading “1 kit issued, Sept” satisfies none of the five.
Clause 2.10.4 closes with an allowance. For authorised medicinal products, alternative approaches may be considered in accordance with local regulatory requirements. The allowance sits with the sponsor and the protocol, and a site applies it only where both agree it in writing. The file holding these records is set out in what belongs in a pharmacy site file.
Where Does the Site’s Duty End and the Sponsor’s Begin?
The site’s duty covers the units in its custody, and the sponsor’s covers the supply that reaches and leaves that custody. Sections 2.10 and 3.15.3 describe two halves of one chain. Clause 2.10.1 lets the sponsor facilitate parts of the site’s work, including forms, computerised systems and arrangements for distribution to participants.
| Activity | The site under section 2.10 | The sponsor under section 3.15.3 |
|---|---|---|
| Getting product to the site | Receives, checks and records the delivery | Supplies the product after approval, timed to avoid interruption |
| Record of the units | Delivery, inventory, per-participant use, and disposition on written authorisation | Identity, shipment, receipt, return and destruction across the study, and the retrieval process |
| Blinding | Follows the randomisation procedure and breaks the code only as the protocol allows | Implements the blinding process and the emergency identification mechanism |
Both record sets describe the same units from two directions, which is why both exist. How the split works in the systems each party runs is set out in which record an RTSM holds and which the pharmacy holds.
Also Read: Who Is Accountable for IMP at a Trial Site?
How Does a Monitor Test Section 2.10 at a Visit?
A monitor tests section 2.10 through the four confirmations in clause 3.11.4.5.3, the monitoring counterpart to the site’s duty. Each maps onto a clause already met or missed.
- Storage conditions are acceptable and match the protocol, testing clause 2.10.5 against the temperature record.
- Supplies are sufficient and within shelf life, testing the expiry field in the 2.10.4 record against the stock on the shelf.
- The correct product went to eligible participants at the protocol dose and in line with randomisation, testing clause 2.10.6 against the prescriptions and allocations.
- Participants and staff received the necessary instruction on proper use, testing clause 2.10.7 against the counselling record.
Clause 3.11.4.5.2 adds a fifth test at close-out, where the monitor confirms the final accountability of the IMP, including return and destruction. Control over these records is a quality system question as much as a pharmacy one, and the site’s quality management system holds the procedures and training behind them. The same integrity expectations are covered for electronic records in how ICH E6(R3) changes the rules for eSource, and where these duties fail in practice shows in the most common MHRA GCP inspection findings.
Section 2.10 describes one continuous record, kept by people whose authority to keep it is part of the evidence. AQ’s electronic pharmacy site file page sets out how AQ approaches pharmacy records as part of one connected site record. Book a live demo to talk through how your pharmacy evidence sits alongside the rest of your study record.
